Case
A man aged in his 40s presented to a dermatology department with an 8-month history of a pruritic, slowly enlarging plaque over his buttocks. His medical background consisted of chronic back pain, and he was not taking any regular medications. He had a family history of psoriasis. He reported that the eruption caused severe pruritus and was affecting his quality of life. He had been applying potent topical steroids to the affected area several times a day for 4 months that resulted in mild relief from the pruritus but no improvement of the eruption.
On examination there was a clearly demarcated scaly erythematous plaque over the central area of the buttocks with pustules present medially (Figures 1 and 2). The rest of his skin was clear, including the groin and feet.
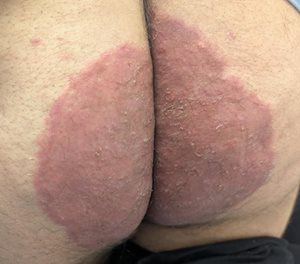
Figure 1. A clearly demarcated scaly erythematous plaque over the central area of the buttocks.
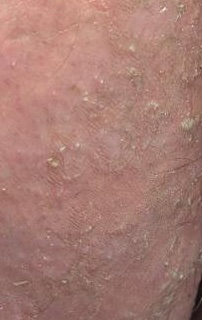
Figure 2. Pustules on an erythematous plaque.
Question 1
What is the differential diagnosis?
Question 2
What investigations should be considered for this patient? Describe the steps involved in completing the relevant investigations.
Answer 1
The differential diagnosis includes psoriasis, contact dermatitis, tinea incognito, candida infection, bacterial infection, fixed drug eruption and extramammary Paget disease.
Answer 2
Initial investigations should include a bacterial swab for microscopy, culture and sensitivity (MCS); a viral swab for herpes simplex virus (HSV) 1, HSV 2 and varicella- zoster virus polymerase chain reaction (PCR); and skin scrapings sent for fungal MCS and/or PCR analysis.
To complete a bacterial swab, the swab should be swiped over the affected areas multiple times. For a viral swab, a sterile needle should be used to pierce and deroof vesicles or pustules, and then the fluid and base of lesions are swabbed. Skin scrapings for fungal MCS should be taken from the edge of the eruption. A small blade should be used at a 90-degree angle to the skin to scrape the scale into a yellow-lid specimen container. If a fungal infection is suspected, it is always important to examine the groin and feet including toenails. If there are any signs of toenail involvement, nail clippings can also be sent for fungal MCS.
If these investigations yield no results, punch biopsies sent for histopathology and culture could be considered and are ideally taken after cessation of topical steroids for several days.
Case continued
Skin scrapings for fungal MCS demonstrated fungal hyphae on microscopy and went on to grow Trichophyton rubrum and Candida species. The viral swab was positive for HSV 1. The bacterial swab was positive for pan-sensitive Staphylococcus aureus 3+.
Question 3
What is the most likely diagnosis?
Answer 3
The most likely diagnosis is tinea incognito with likely secondary bacterial, viral and candidal infection.
Tinea incognito refers to a fungal skin infection when the clinical appearance has been transformed because of the use of topical or systemic immunosuppressive medications.1 In this case, because of long-term topical steroid application, the plaque did not have the classic dermatophyte appearance of peripheral scale with a central zone of clearing. Another clue to active infection is that the plaque continued to slowly increase in size despite ample use of topical steroids. The use of topical steroids suppresses inflammation, allowing for fungal, bacterial or viral growth.2 In this case, the eruption likely originated as tinea corporis; however, after regular topical steroid application, the appearance was altered and the fungal infection, as well as secondary bacterial and viral infections, flourished. Regarding treatment of tinea incognito, the topical steroid used should be ceased and antifungal therapy (ie topical, oral or a combination) should be commenced.3
Case continued
The patient was advised to cease use of topical steroids and was commenced on griseofulvin at initial review. After results of the swabs were available, the patient was contacted and subsequently completed a course of oral antibiotics, oral antivirals and topical miconazole. We decided to treat the bacterial infection because the swab was strongly positive (3+ growth) and there were signs such as significant erythema and pustules present. An alternative option would have been completing a course of antifungal treatment and following up closely to assess response. At a follow-up appointment, the plaque had improved significantly, and post-inflammatory pigmentation was noted (Figure 3). The patient reported that the pruritus had completely resolved and he was now able to complete his activities of daily living without any skin concerns.
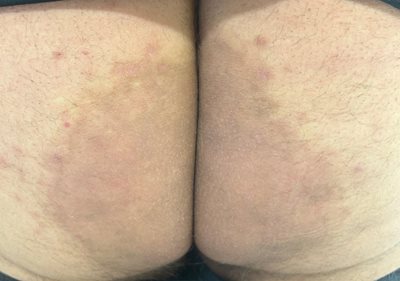
Figure 3. Resolving eruption post treatment.
Key points
- Tinea incognito refers to a fungal skin infection when the clinical appearance has been altered because of the use of topical or systemic steroids or other immunosuppressive medications.1
- Failure to respond to treatment might indicate misdiagnosis and should prompt further investigations. Skin swabs and scrapings are straightforward to complete and might provide a diagnosis and prevent the need to undertake more invasive investigations.
- Prolonged use of topical steroids increases risk for superimposed bacterial, viral and fungal infections.2