Discussion
This is a case presentation of a man aged 82 years with LM involving most of the scalp. Multiple shave biopsies demonstrated only in situ disease, yet complete excision revealed a focal desmoplastic melanoma (Breslow thickness 5.5 mm). The invasive component was entirely subclinical and undetected on prior sampling. This case illustrates the danger of undertreating invasive disease if topical therapies such as imiquimod or radiotherapy are used. Surgical excision remains the gold standard, and general practitioners play a pivotal role in recognising when referral is required.
Lentigo maligna (LM) typically presents as a slowly growing pigmented lesion on sun-damaged skin in older adults.1 General practitioners (GPs) are often the first to assess and manage LM, and decisions regarding referral, treatment and follow-up frequently fall within primary care. Management becomes particularly challenging when lesions are extensive or located on cosmetically or functionally sensitive sites. Non-surgical options such as topical imiquimod and radiotherapy are increasingly considered, particularly in elderly or medically frail patients.2 The success of these approaches depends on confidently excluding invasive disease, as partial sampling might miss detection of invasive melanoma, limiting the safety of non-surgical approaches.2,3
Desmoplastic melanoma (DM) is a rare melanoma subtype that can arise within LM and can be clinically and histologically subtle yet carries important treatment implications.3–5 We present a case of DM arising within a large scalp LM that was not detected on multiple mapping biopsies, highlighting key considerations for diagnosis, referral and management in general practice.
Case
A man aged 82 years presented with an enlarging pigmented lesion on the scalp, measuring approximately 10 × 15 cm at the time of review, with variegated pigmentation and background actinic damage (Figure 1). Dermoscopy demonstrated irregular pigmentation and areas of regression within a background of actinic damage, but no obvious invasive focus was identified (Figure 2). Seven mapping biopsies to mid-dermis were performed, targeting clinically suspicious and representative areas. These demonstrated extensive LM with atypical junctional melanocytic proliferation, together with solar keratosis and in situ squamous cell carcinoma. No invasive melanoma was identified.
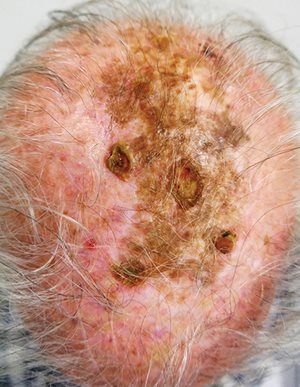
Figure 1. Extensive lentigo maligna of the scalp, with irregular pigmentation and actinic damage. Multiple mapping biopsies showed only lentigo maligna and solar keratosis.
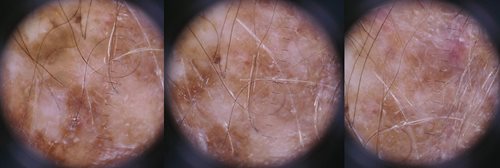
Figure 2. Dermoscopy findings of irregular pigmentation and areas of regression within a background of actinic damage.
The case was reviewed at the local hospital’s multidisciplinary melanoma meeting. The patient was functionally independent with limited comorbidities and good cardiovascular fitness, and he was considered suitable for a short general anaesthetic. Management options, including topical imiquimod, radiotherapy, observation and surgical excision, were discussed. The patient elected to proceed with surgical excision.
The lesion was widely excised under general anaesthesia, with the depth of excision extending to the periosteum. Reconstruction was performed using a split-thickness skin graft. Histopathological examination revealed extensive LM with a focal DM (Breslow thickness 5.5 mm, Clark level IV) in a fibrotic stroma (Figures 3 and 4), together with background in situ squamous cell carcinoma and seborrhoeic keratosis. Surgical margins were clear (30 mm peripheral, 0.9 mm deep). The patient recovered uneventfully and at 5-year follow-up remains disease-free with no evidence of local or systemic recurrence (Figure 5).
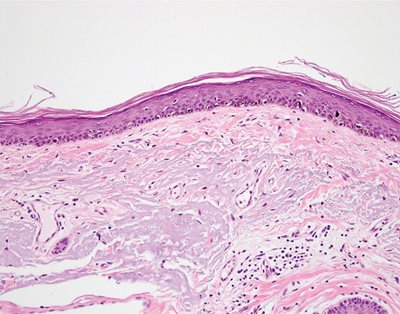
Figure 3. H&E section demonstrating atypical melanocytic proliferation along the dermoepidermal junction, consistent with lentigo maligna. There is one zone of cellular fibrosis and patchy lymphocytic inflammation, which extends through the dermis and into the subcutis. In this region there are plump spindle cells set between sclerotic collagen bundles.
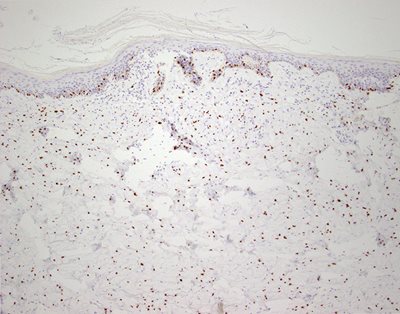
Figure 4. SOX10 immunostaining highlighting intradermal spindle cells, confirming the diagnosis of desmoplastic melanoma.
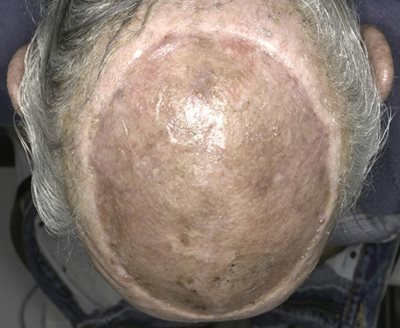
Figure 5. Healed scalp following wide local excision and split-thickness skin graft reconstruction. The patient experienced no local recurrence and remains disease-free at 5-year follow-up.
Discussion
DM is an uncommon melanoma subtype characterised by spindle cell morphology and a fibrotic stroma,3 accounting for approximately 2–4% of cutaneous melanomas in Australia.5 Clinically, it often lacks the typical features of melanoma, presenting as amelanotic or hypopigmented lesions, which are easily overlooked.4 DM arises predominantly on chronically sun-damaged skin in older adults, most often diagnosed in the seventh and eighth decades of life, and it is not uncommonly associated with LM.3 Although the precise relationship between LM and DM remains uncertain, their coexistence is well recognised.3–5
A recent Australian review by Hughes et al highlighted the diagnostic challenges and management considerations for DM in clinical practice.5 Dermoscopy, recommended in current guidelines, assists in biopsy targeting and in detecting amelanotic or hypopigmented areas that might harbour invasion.5 Reflectance confocal microscopy can further improve diagnostic accuracy and margin assessment, although access is generally limited to specialised centres.5
In clinical practice, the risk of invasive melanoma increases with larger or atypical LM lesions.6–9 In a large retrospective cohort, Raghavan et al9 reported that 58.6% of DMs were associated with LM, most often occurring in older patients, on head and neck sites, and in larger lesions. This aligns with our case of a large scalp LM with DM arising as a small, focal invasive component within a broader in situ lesion. Such presentations highlight the limitations of partial biopsy, which carries a risk of missing occult invasion.8,9 For this reason, surgical excision remains the gold standard, providing both definitive diagnosis and treatment.8–10
Australian guidelines recommend complete surgical excision for LM with 5–10-mm margins where feasible.8 Large lesions should not be presumed inoperable in general practice; timely referral to a plastic surgeon allows assessment of reconstructive options and preserves the opportunity for curative surgery.7 When patients are hesitant, the reasons should be explored, as reluctance is often based on misconceptions about morbidity or disfigurement. In reality, reconstructive techniques frequently achieve good cosmetic and functional outcomes, and cure rates for surgical excision are significantly higher than for alternative treatments.6,8 For LM specifically, staged excision and Mohs micrographic surgery have demonstrated lower recurrence rates when compared with standard excision, particularly for facial lesions.5,11 However, these techniques are not widely available, and standard excision remains the most accessible and practical approach in general practice.
Topical imiquimod has demonstrated efficacy for LM in selected cases, with reported clearance rates of 76–85%; however, follow-up is typically short (median 2 years), and long-term efficacy remains uncertain.9–13 Radiotherapy might achieve comparable or higher clearance rates, but late complications including skin atrophy, impaired wound healing and a small risk of secondary malignancy require careful consideration.6,13 Early results from the radiotherapy versus imiquimod for lentigo maligna (RADICAL) trial reported approximately 90% clearance at 27 months post-randomisation, with comparable short-term efficacy for imiquimod and radiotherapy.14 Despite these uncertainties, imiquimod is increasingly prescribed in general practice, particularly in elderly patients or for lesions in difficult anatomical locations.2,10,14 Although appropriate in carefully selected cases, its apparent simplicity might provide a misleading alternative to surgery and risk undertreating patients with invasive disease.9 In selected frail patients, active monitoring might also be a reasonable option, provided careful clinical and dermoscopic follow-up is undertaken and invasion can be confidently excluded.5 Nonetheless, for large or atypical LM, referral to a multidisciplinary team remains essential to guide management, particularly where surgery is not feasible or is declined despite counselling and non-surgical options are being considered.2–4
Conclusion
This case underscores the heterogeneity and management complexity of LM, reinforcing the importance of timely referral to clinicians with expertise in dermoscopy and, where available, advanced imaging to ensure optimal care. Large or atypical LM lesions carry a risk of harbouring invasive melanoma, which might be missed on biopsy because of sampling limitations. Surgical excision, therefore, remains the most reliable management strategy, offering both definitive diagnosis and treatment. Referral for surgical assessment should precede consideration of non-surgical alternatives. From a GP perspective, topical imiquimod should not be considered a first-line treatment for LM and should only be undertaken following multidisciplinary consensus.
Key points
- DM is an invasive melanoma subtype not uncommonly associated with LM.
- Partial biopsy might miss focal invasion, particularly within large LM lesions.
- Surgical excision remains the gold standard. Large lesions, especially on cosmetically or functionally sensitive sites, should not be deemed inoperable without surgical assessment.
- Imiquimod or radiotherapy should only be considered for LM following multidisciplinary review.