CASE 1
A well girl, aged 15 months, presented with a flesh‑coloured protruding lesion on the perineum (Figure 1), which was noticed by her mother 1–2 months earlier. Her only relevant history was intermittent constipation. The lesion measured 12 mm.

Figure 1. Case 1: Tongue-like protrusion on the perineum of a girl aged 15 months.
Case 2
A well girl, aged 10 months, presented with a flesh‑coloured perineal protrusion (Figure 2), without associated symptoms. The lesion was noticed a few weeks prior, and measured 8 mm.
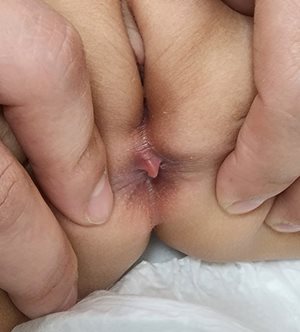 Figure 2. Case 2: Pyramidal-like protrusion on the perineum of a girl aged 10 months.
Both lesions appeared as a solitary, soft, pyramidal or tongue‑like protrusion located in the midline anterior to the anus. The surfaces were smooth, pink–red to flesh‑coloured, with no ulceration, bleeding or tenderness. There were no signs of perianal trauma, fissures, discharge or infection. In both cases, there was no history suggestive of sexual abuse.
Question 1
Based on the above clinical information, what are the likely differential diagnoses?
Question 2
What is the most likely diagnosis and its characteristic features?
Answer 1
The likely differentials include:1–3
- Skin tag or perineal skin fold: usually a pedunculated or sessile soft papule. Although age and location can overlap, these lesions are often lateral rather than strictly midline.
- Infantile perineal (perianal) pyramidal protrusion (IPPP): classically presents as a solitary, midline protrusion anterior to the anus in young female children.
- Haemangioma: typically red to violaceous, compressible and vascular in appearance, rather than a solid, flesh‑coloured nodule.
- Rectal prolapse and haemorrhoids: mucosal, often circumferential tissue protruding through the anal verge, usually associated with straining and sometimes bleeding.
- Condylomata acuminata: multiple verrucous papules caused by human papillomavirus.
- Findings related to sexual abuse: these are rare and are usually accompanied by additional signs such as fissures, bruising or scarring, rather than an isolated, stable midline lesion.
Answer 2
The most likely diagnosis is infantile perineal (perianal) pyramidal protrusion (IPPP). IPPP is a benign soft‑tissue perianal protrusion, ranging from 0.5 to 3 cm in size.1,2 It typically presents as a solitary, midline lesion with a pyramidal, tongue- like, leaf-like, hen’s-crest- like or peanut-like shape.1,2,4 The protuberance is pink–red or flesh‑coloured, commonly located anterior to the anus in otherwise well infants and young children.2,5
IPPP was first described in 1989 by McCann et al as a ‘perianal soft-tissue, acrochordon-like protrusion’, highlighting the importance of recognising this benign condition when evaluating possible sexual abuse.6 The formal term ‘infantile perianal pyramidal protrusion’ was later introduced by Kayashima et al in 1996.7 In the literature, the terms perianal and perineal are used interchangeably, with no clear consensus.8,9 Some authors favour the term ‘infantile perineal protrusion’ as not all lesions are strictly pyramidal in shape.4
IPPP can be present from birth to age 5 years, but most cases present and are diagnosed between 8 and 15 months, with more than 90% occurring in female infants.1 No racial predilection has been observed, with reported cases spanning various continents.1,2,4,5 The true incidence and prevalence remain difficult to establish because of presentation to various clinicians, nomenclature and the often asymptomatic nature. It is usually noticed by caregivers during nappy changes.
Question 3
What causes IPPP and how is it diagnosed?
Question 4
How is IPPP managed?
Answer 3
The exact aetiology of IPPP is not fully understood, but several mechanisms have been proposed. These include anatomic weakness along the perineal median raphe, chronic mechanical irritation from wiping or friction, constipation and straining, and a possible association with lichen sclerosus in a minority of cases.1,3 Although constipation is frequently reported, its causal role remains unclear.
Diagnosis is primarily clinical, based on the characteristic features. Biopsy is usually neither ideal nor necessary. In cases of significant diagnostic uncertainty, ultrasonography can be considered, which might show a thick hypoechoic area of skin with increased power Doppler signal, reflecting hypervascularity.10
Answer 4
IPPP is a benign, self‑limiting condition, and treatment is usually not required. Reassurance of caregivers is central, along with attention to constipation management, if relevant.1–3 Topical petrolatum (Vaseline, Unilever Australia [NSW] & New Zealand [Auckland]) or a corticosteroid can be used to minimise friction and bleeding, if present. Spontaneous resolution usually occurs over weeks to months, and in some cases, can take more than a year.1–3
Clinical outcomes
Case 1 received constipation management (dietary advice and stool softeners) and topical petrolatum was recommended. Referral to a paediatric specialist was provided also, at parental request. The lesion resolved within 6 months. Case 2 resolved spontaneously over approximately 1 year without specific treatment.
Discussion
IPPP is a benign perineal lesion occurring in early childhood that can mimic more concerning conditions, such as rectal prolapse, haemorrhoids or signs of sexual abuse, leading to parental anxiety and potentially unnecessary investigations or treatment.
These cases illustrate typical presentations of IPPP in young girls, with no other perianal pathology and spontaneous or gradual improvement without invasive intervention. Awareness of IPPP enables clinicians to make a confident clinical diagnosis, provide reassurance, implement simple supportive measures and arrange appropriate follow‑up, thereby avoiding invasive procedures and unwarranted escalation of care.
Key points
- IPPP is a benign, self‑limiting lesion that typically affects infant girls.
- Recognition of the characteristic solitary midline protrusion anterior to the anus helps distinguish it from other mimicking conditions.
- Increased awareness of IPPP can reduce misdiagnosis and prevent unnecessary investigations or inappropriate management.