People living in larger bodies are vulnerable to weight stigma when accessing maternity care.1 Weight stigma is defined as the negative attitudes, beliefs and stereotypes about people based on their body size, and is pervasive in the medical system.2,3 Resting on the assumption that larger bodied people are gluttonous, lazy and lacking self-discipline, weight stigma can cause physical and psychological harm, and affected individuals are less likely to access or receive adequate care.4 A direct contributor to ‘the global obesity pandemic’,5 weight stigma is particularly harmful in maternity care, where it can overshadow the joy and miracle of childbirth. While maternity care providers aim to deliver the highest quality care, stigmatising attitudes about body size can negatively affect their provision of care, leading to patient disengagement and, ultimately, worse outcomes for mother
and baby.3,6
In Australia, a general practitioner (GP) is often the first healthcare professional that a woman sees in her journey through pregnancy, the one who manages her antenatal and postnatal care, and who cares for her baby as it grows. Integral to maternity care, GPs hold responsibility for initiating non-stigmatising care for people of all shapes and sizes.
While there is increasing recognition that weight-based bias and stigma are major obstacles in efforts to advance prevention and treatment of illnesses associated with larger bodies,7,8 there is limited evidence regarding approaches that produce sustained attitude and behavioural change among clinicians.9 Input from GPs is key to the development of successful interventions. To date, however, there has been little research investigating the views of GPs on weight stigma in maternity care. Most research has employed quantitative surveys, focused on consumer voices, or the negative stigmatising views of healthcare practitioners.5,10,11
Using non-stigmatising language is important, as inappropriate language can, often unintentionally, have a detrimental impact.2 In this paper, we have occasionally used the word ‘fat’. Many individuals and communities have reclaimed the word as a source of empowerment and resistance and as a neutral descriptor rather than a derogatory term.12 More often however, we have used the phrase ‘larger bodied’. We have made a conscious effort to avoid terms such as ‘overweight’ and ‘obesity’, as we agree with fat activists and scholars that medicalising body shape and size adds to stigma.9 We use the term ‘women’ as all our participants and most maternity patients in Australia identify as such. However, we acknowledge that not all people who seek and receive prenatal, antenatal and postnatal care identify with the term. We intend to be inclusive of all people who are pregnant or give birth, guided by literature where gendered language has been used.13,14
This study aimed to explore the views of GPs with high fat acceptance on weight stigma in maternity care, to inform meaningful recommendations for practice, policy and educational reform.
Methods
The Maternity care providers’ attitudes and beliefs toward weight and body size during pregnancy (Mat-CARES) survey was conducted in 2023–24,15 measuring the implicit and explicit weight bias of maternity care providers using the Fat Attitudes Assessment Toolkit (FAAT), a validated measure for quantifying contemporary attitudes towards fat people and fatness (Box 1).16 Survey data enabled calculation of a Fat Acceptance Composite (FAC) score, with a higher score indicating a more positive evaluation of larger bodied people.
|
Box 1. FAAT and FAC
|
|
The FAAT measures contemporary fat attitudes and beliefs in a non-stigmatising manner. There are nine subscales, eight of which were used in the Mat-CARES survey: (1) empathy (7 items); (2) activism orientation (7 items); (3) size acceptance (6 items); (4) critical health (5 items); (5) general complexity (6 items); (6) socioeconomic complexity (3 items); (7) responsibility (6 items); and (8) body acceptance (4 items). We excluded the ‘attractiveness’ subscale, as this was not relevant to our research question. Responses utilise a 7-point Likert scale, with higher FAC scores indicating higher levels of fat acceptance and more positive evaluations of larger bodied people.16
FAAT, Fat Attitudes Assessment Toolkit; FAC, Fat Acceptance Composite; Mat-CARES survey, Maternity care providers’ attitudes and beliefs toward weight and body size during pregnancy survey.
|
A total of 144 GPs responded to the Mat-CARES survey, and 49 of these indicated a willingness to be contacted for further research. Purposive sampling was utilised to select GPs with higher fat acceptance, and therefore lower implicit and explicit weight bias, to implement a strengths- based approach.17
The FAC scores of the GPs ranged from 25 (highest) to 7 (lowest), with a mean score of 22.74. The GPs with a score of 20 or above (n = 34) were invited via email to participate in a semi-structured interview over videoconference (Zoom Communications, San Jose, CA, USA), and 25 of these GPs agreed to interview. Between May and July 2024, 20 interviews were conducted before adequate information power was considered to have been reached.18 Interviews were conducted by JVDH, a general practice academic registrar with a Diploma of Obstetrics and Gynaecology (DRANZCOG) and with recent experience of receiving maternity care. The question guide was developed to elicit an understanding of participants’ backgrounds, beliefs and behaviours when caring for larger bodied maternity patients (Appendix 1; available online only). Interviews were recorded on Zoom with permission and transcribed verbatim.
Data analysis
Data was analysed using Braun and Clarke’s Reflexive Thematic Analysis (RTA), in order to embrace JVDH’s own subjectivity and creativity as assets in knowledge production.19 Coding involved identifying comments that addressed similar issues, and then organising these around relatively core commonalities to form overarching themes. Multiple additional coders were utilised (LC, KW), not to pursue consensus, but to reflexively sense-check and explore interpretations.19 Reasoning was inductive, attempting to create latent meaning from the data.
Ethics approval
Ethical approval was provided by The University of Queensland Ethics Committee (project ID 2023/HE001582). This research was undertaken with the informed consent of participants. In respectful recognition of their time, participants were offered a $150 gift card.
Findings
Twenty GPs from six Australian states and territories were interviewed. The mean interview time was 18 minutes (range 9–31 minutes). Seventeen participants were based in metropolitan areas, and three practiced procedurally as GP obstetricians. The median self-identified body shape was 5.5 on the 9-point Stunkard Scale20 (Figure 1). All participants identified as female and non-indigenous and fifteen were parents (Table 1).
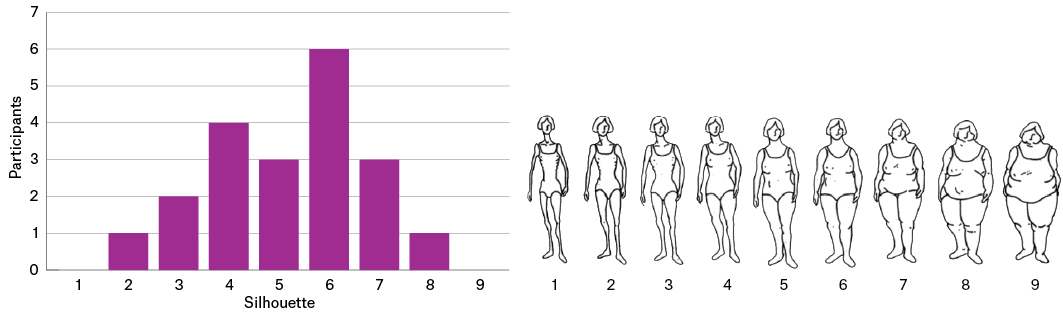 Figure 1. General practitioner participants’ self-identified body silhouette using Stunkard scale.20 Click to enlarge.
|
Table 1. Demographics of general practitioner participants (n = 20)
|
|
Demographic
|
Percentage (n)
|
|
Age range
|
|
31–40 years
|
75% (15)
|
|
41–50 years
|
20% (4)
|
|
51–60 years
|
5% (1)
|
|
Profession
|
|
GP
|
85% (17)
|
|
GP obstetrician
|
15% (3)
|
|
Location
|
|
Metropolitan practice (MMR 1)
|
80% (16)
|
|
Rural practice (MMR 3–5)
|
10% (2)
|
|
Remote or very remote practice (MMR 6–7)
|
10% (2)
|
|
Years practising
|
|
<5 years
|
5% (1)
|
|
6–10 years
|
50% (10)
|
|
11–15 years
|
35% (7)
|
|
>15 years
|
10% (2)
|
|
Children
|
|
Has children
|
75% (15)
|
|
Does not have children
|
25% (5)
|
|
GP, general practitioner.
|
|
Six themes were constructed from the interview data: (1) personal journey; (2) socioeconomic environment; (3) uncertainty; (4) harms; (5) beneficence; and (6) recommendations (Figure 2). These are discussed below under three headings: personal experience of weight stigma; professional experience of weight stigma; and recommendations for reducing weight stigma.
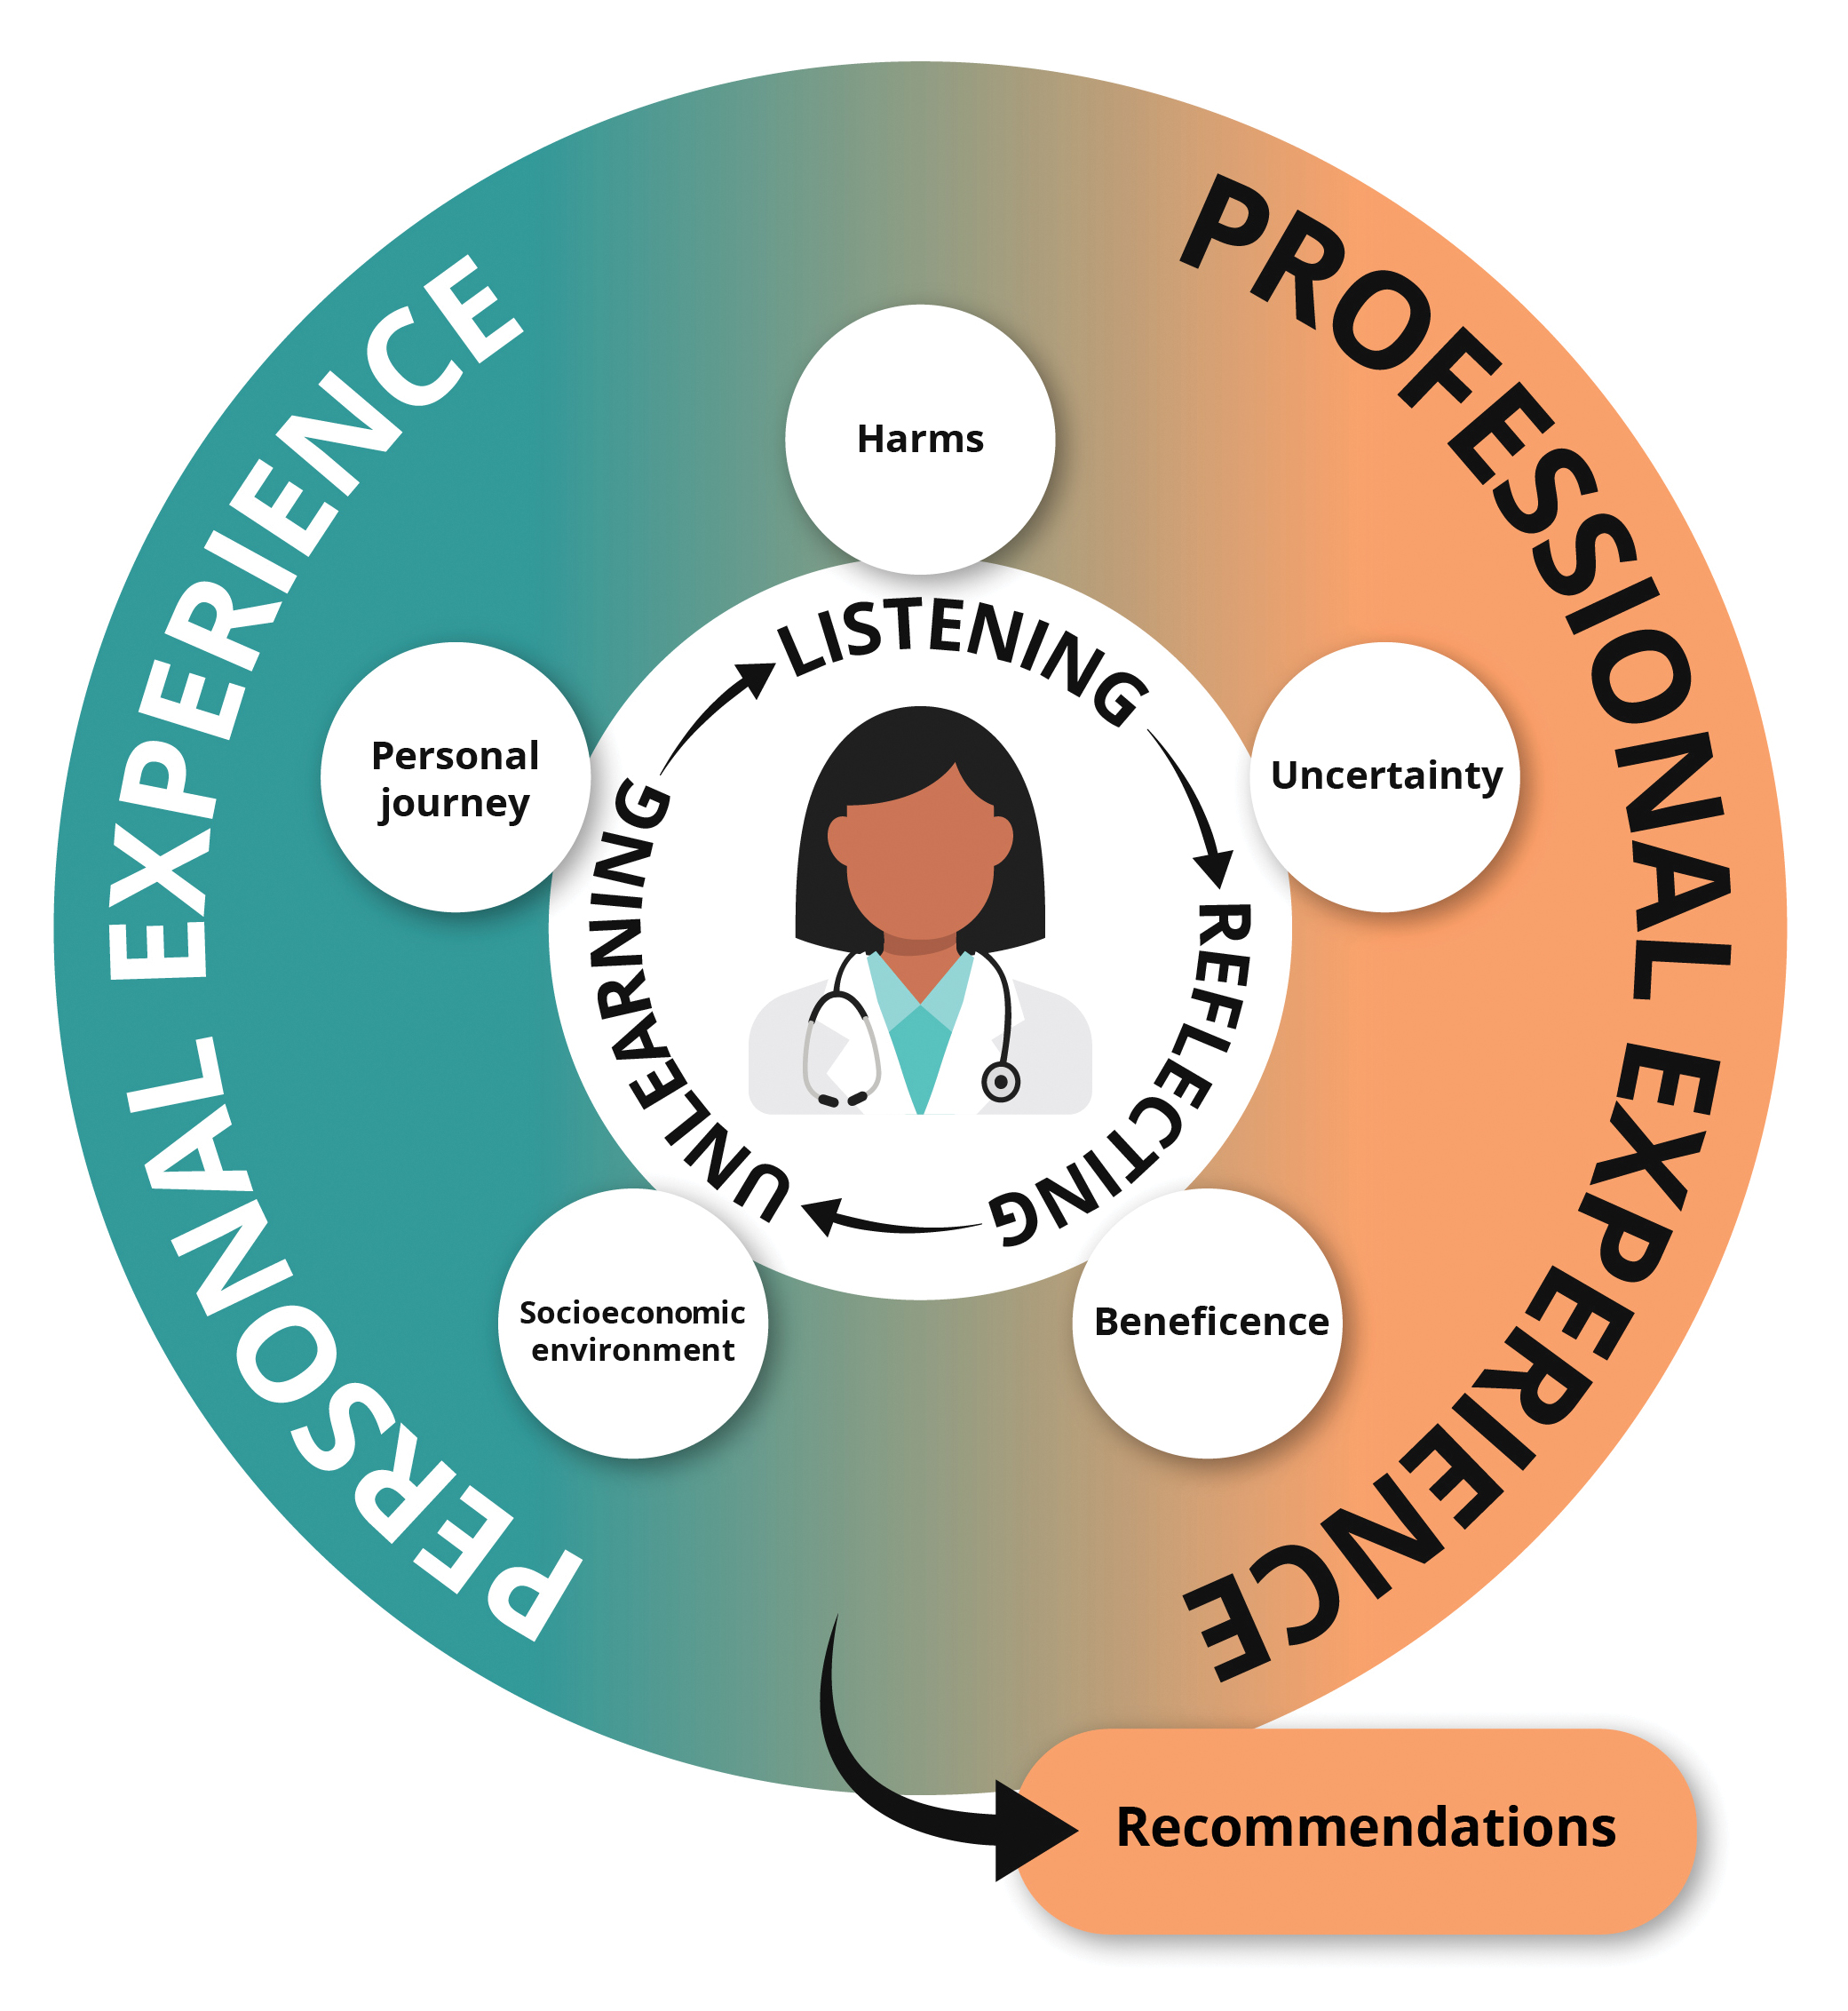
Figure 2. The general practitioner experience of weight stigma in maternity care: an ongoing journey of listening, reflecting and unlearning.
Personal experience of weight stigma
Personal journey
Personal struggles with weight and body image strongly influenced GP views on weight stigma. For some (9 participants), this was due to their experience of living in a larger body:
I’ve been overweight my entire life … So I kind of experienced bias and stigma from a very young age. (GP01)
For others, it was struggles with body image or disordered eating in earlier years, or witnessing the struggles of a loved one:
I have personal experiences with disordered eating. Going through that made me more receptive to a different approach. (GP17)
For many, their interest in the issue of weight stigma was triggered by the experience of becoming a parent themselves. Pregnancy and postpartum are periods when an individual’s ‘body completely changes’ (GP16), and bystanders might feel that they have a free pass to comment on these changes. For many, especially those who do not ‘get back to pre-pregnancy size within 12 months’, this can be a ‘really hard time’ (GP16).
Three GPs who had female children that are now either pre-teen or teen described the challenges involved with parenting in a space with a heavy influence of body image as being instrumental in their changing of attitudes:
Having a daughter was instrumental … because I didn’t want her to feel as bad about her body as my friends all did … I didn’t want that to happen for another generation. (GP19)
Interestingly, these same GPs reflected on their own experience of being a daughter and having their body criticised:
I remember my own late mother mirroring, I’m sure, what happened to her, commenting when she thought I was looking less or more thin or less or more fit, and I didn’t like it. (GP05)
The GPs were honest about their limitations in achieving completely weight‑neutral attitudes, citing that they still need to ‘stop and check’ themselves (GP03) when they become critical of body weight. They admitted that their journey to body acceptance remains ongoing and unfinished:
I’m pretty sure there’s a long way for me to go, but I think that’s a good start. (GP10)
Socioeconomic environment
Multiple GPs made reflections on growing up in a society where diet culture and fat shaming are pervasive, and the negative impact of this on body image and self-worth. They reported the sentiment ‘fat equals unhealthy, skinny equals healthy’ (GP08) was strongly perpetuated by the media, peers and healthcare professionals during their younger years and when receiving their own maternity care. While this sentiment remains alive and well in today’s society, positive changes over time were noted by an older GP, who has seen ‘strong’, rather than ‘skinny’ women become role models for today’s generation.
Further quotations relating to GP personal experience are presented in Appendix 2 (available online only).
Professional experience of weight stigma
Harms
All participants commented on the harm that they have seen weight stigma cause the women they care for.
Emphasis was placed on mental health harms, in particular the damaging effect of shame on women, stemming from a society and a medical profession that traditionally links health and self-worth to a number on a scale:
They’ve got mirrors. They know that they’re overweight. I’m not sure ramming it home with the number on the scale is really going to make a lot of difference. They already know. They all suffer, most of them, not (sic) everyone, but a lot of them suffer with a huge amount of shame anyway. (GP19)
Witnessed stigmatising events had often taken place in hospital settings, however participants also mentioned the harm caused by doctors who recommend weight loss to larger bodied patients at every consult, even if the presenting complaint had nothing to do with weight.
Participants highlighted that psychological conditions and eating disorders are often linked with living in a larger body, and that these can be made worse by perceived judgements from healthcare professionals:
So that’s a really big deal. If we, as healthcare providers are, inadvertently I’m sure, triggering people’s eating disorders through our language and behaviours. (GP14)
Crucially, it was emphasised that these mental harms are avoidable, and that they ultimately lead to inadequate maternity care; through missed diagnoses, overly simplistic pathophysiology, conflicting advice, and ultimately, disengagement from healthcare.
Participants expressed frustration with the lack of holistic teaching on weight and body size in medical education and the way ‘weight’ often serves as a proxy for ‘health’. While the GPs still use body mass index (BMI) when required (eg for hospital referrals), most reported dissatisfaction with the measure: ‘BMI is a terrible indicator of health’ (GP03). GPs noted situations where women had been pigeon-holed, unnecessarily over investigated, or not believed by other health professionals. GP11 said, ‘it’s not always gonna be the fat person who gets GDM (gestational diabetes mellitus)’.
Women being given conflicting advice was raised as an issue by participants, for example in situations where women are told to delay pregnancy until they ‘lose weight, but also don’t start trying too late … it’s a bit of a hard ask’ (GP06).
Participants emphasised that these inadequacies could become very harmful when they cause women to disengage from healthcare:
… we want people to engage in care, and we all know that antenatal care is an important part of providing safe care for mums and babies, and if we’re pushing women away, then that can only have negative consequences. (GP14)
Uncertainty around the right way to practice
However, participants acknowledged that larger bodies in pregnancy can be associated with increased health and/or safety risks, such as gestational diabetes and caesarean delivery. These were particularly noted by GP obstetricians who practice rurally and therefore are responsible for procedures, such as deliveries and caesarean sections, which can be more technically challenging and carry higher risks for larger bodied women:
I often … become quite stressed doing antenatal clinic or deliveries for women with larger bodies as it is often more challenging. (GP02)
Rural practitioners face additional challenges because of the lack of available resources for handling difficult emergency situations, and highlighted the stress involved in dealing with these away from collegiate and equipment support. They therefore expressed understanding of policies requiring women over certain BMI cutoffs being transferred to tertiary centres, however still felt that such policies can be stigmatising.
In the face of such challenges, both rural and metropolitan participants expressed a desire to be pragmatic; however, doing this in a space with unclear and sometimes outdated guidelines leads to stress and uncertainty. Many GPs admitted to disregarding guidelines and practising in a way that felt least stigmatising to them. This led to differences in practice between the GPs interviewed:
It’s about marrying the two because there’s formal teaching and knowing there’s a gap in the evidence, so you’re sort of finding a way that works for you to practice. (GP06)
A good example of this is the practice of weighing women at every antenatal visit. Many participants never weighed, some weighed only to support a hospital referral and one weighed every woman at her initial visit. Some felt comfortable going against guidelines, while for less experienced GPs this led to further uncertainty.
Ethical duty: Beneficence
The key motivation for GPs to practice weight-neutral maternity care, even when this means ignoring guidelines, is the duty to do what is right for the patient (beneficence):
The answer is simple: (it’s) be respectful.
I think that’s just the crux of what it
should be. (GP18)
Participants emphasised a holistic view of health, expressing that the focus of care should be on ‘the whole woman’ (GP08), encouraging nourishing food, enjoyable physical activity and strong social networks to support mental health; regardless of weight or size. Through this, GPs felt they have ‘been able to engage in better healthcare outcomes for people because we’re not focusing on a number’ (GP16).
Several GPs suggested that best practice care starts with meeting women where they are at, rather than pushing their own agenda on her. They said that the role of the GP is to support the woman within the parameters that they have, particularly during the already emotionally heightened and sensitive period of life that is pregnancy.
In their desire to provide good care, some GPs saw themselves as protectors of their patients, often feeling it was their duty to warn them about, and support them through, the stigma and bias that they might receive from other healthcare professionals during their maternity care.
Further quotations relating to GP professional experience are presented in Appendix 3 (available online only).
GP recommendations for reducing weight stigma in maternity care
Critical reflection was pivotal in the journey of ‘unlearning’ (GP19) that led these GPs to become more fat accepting. The GPs recommended that others hoping to provide non-stigmatising maternity care could reflect on their own personal and professional experiences and how these have potentially led to anti-fat biases:
I’ve reflected on how much work I’ve put into this, thinking … ‘no wonder other GPs don’t have this view because of what we’re taught.’ And because it has taken such a significant amount of self-reflection and reflection on society as a whole. (GP04)
They recommended seeking educational opportunities outside of the traditional teachings, citing frameworks such as ‘Health at Every Size’ (HAES), and clinician led social media groups such as ‘GP Mums’, which had been beneficial for them.
GPs recommended a number of organisational changes to decrease weight stigma in maternity care. These included revising evidence-based guidelines on caring for larger bodied women, research to better understand the epidemiology of obesity and pregnancy outcomes, and appropriately representing risk (relative vs absolute). They advocated for communication skills training built on language consensus, for example writing cases with larger bodied patients for difficult communication registrar training days or Objective Structured Clinical Examination (OSCE) stations. They recommended investing in appropriate equipment and upskilling clinicians to ensure safe physical clinical environments, and increased funding for rural and regional areas.
Further quotations highlighting GP recommendations are presented in Appendix 4 (available online only).
Discussion
Three key findings emerged from this study:
- GPs have experienced the harms that weight stigma causes; either to themselves, a loved one or a patient.
- Despite acknowledging the difficulties that can arise when treating larger bodied people, the GPs interviewed have been able to increase their fat acceptance through extensive reflective practice.
- GPs feel a duty to do what is right for their patients, and thus have shared recommendations, including revising guidelines, communication training
and increased funding to rural and
regional areas.
This is the first study to explore GP views on weight stigma in maternity care with a strengths-based approach. Nevertheless, our study has two main limitations. Firstly, our study was a purposely selected, convenience sample of entirely female and non-indigenous GPs, and therefore findings might not be generalisable. This is an important limitation, given that gender and cultural context can shape both health experiences and access to care. The predominance of women likely reflects both the topic’s relevance and broader participation patterns but highlights the need for more inclusive recruitment strategies in future research to ensure diverse perspectives are captured. Purposively selecting GPs with the highest FAC score did, however, allow us to employ a strengths-based approach and focus the interviews to be solution driven. In this though, the second limitation appears. The second main limitation is that we have assumed that GPs who are the most fat-accepting are also providing more fat-accepting care, which is not a proven hypothesis. To know if this is true, we need to investigate the experience of the patients of the GPs with higher FAC score.
Conventional weight-centric medicine is, at best, incomplete. Our results concur with those of previous studies that report the harmful presence of weight stigma in healthcare, and call for the development of clear guidelines and increased training opportunities for healthcare professionals.5,7,9 The novel contribution of our research lies in its focus on everyday primary care practitioners with a low anti-fat bias, allowing us to learn from GPs on the frontline of maternity care. The recommendations of our participants have been summarised into practical solutions, presented in Box 2.
|
Box 2. Practical solutions for GPs navigating the uncertainties of treating larger bodied maternity patients
|
- Understand your own level of implicit weight bias.
- Take the time to engage in a deep critical reflection of your own background and beliefs about larger-bodied people, and how this might affect your behaviour in clinical practice.
- Seek out educational opportunities that promote new models of thinking about weight and body size. Refer to references 22–25 for some suggested articles to start with.22–25
- Consider your language use. We suggest the phrase ‘larger-bodied’, and welcome feedback on this.
- Use discretion when weighing women. Regular weighing has no evidence of an effect on clinical outcomes.25 We suggest having scales hidden from view, and only weighing if requested by the woman.
- Use documentation to advise other clinicians not to discuss weight (eg in the chart include ‘patient aware of weight, please do not discuss further without consent’).
- GP educators to teach students and registrars respectful communication skills. Suggest a weight stigma station in a difficult communication OSCE station.
- GPs involved with guideline writing to review or rewrite maternity guidelines to:
- reduce use of BMI and replace with more appropriate measures8,26
- include efficient summaries of robust, up-to-date evidence on maternity outcomes for larger bodied patients
- use accurate representation of risk (ie use absolute rather than relative risk).
- Call on policymakers to better support rural and regional practitioners, with investments in on-ground skilled teams, and funding for appropriate equipment.
BMI, body mass index; GP, general practitioner; OSCE, objective structured clinical examination.
|
Reflective practice that allows healthcare practitioners to recognise their weaknesses and identify knowledge and skills gaps is crucial in overcoming weight stigma in healthcare.21 The GPs that we interviewed appear to have reduced their own weight‑based biases. Importantly, they have achieved this through an entirely self-directed journey of critical reflection, unlearning and relearning. To our knowledge, this is the first evidence that GPs have been able to reduce their own weight-based biases through self-directed reflective practice.
Conclusion
The GPs interviewed have engaged in reflective practice that has enabled them to reduce their own weight-based biases. Strategies they used to achieve this included reflecting on their upbringing and personal experiences, reflecting on the harms weight stigma caused their patients, and engaging with educational resources outside of the traditional medical curriculum. Teaching weight-inclusive maternity care alongside communication skills to medical students and general practice registrars is vital. A guideline for weight-inclusive maternity care that summarises up-to-date and robust evidence would be beneficial. Investment should be made in weight-inclusive skills and communication training, and mental health supports; especially in rural areas. Future research should determine how best to support educators, policymakers, students and practitioners to reflect on their own experiences and biases to make changes to promote inclusive maternity care for people of all shapes and sizes.