This article is part of a series of articles on doctors’ health and wellbeing.
For some time, the occupational wellbeing of general practitioners (GPs) has been recognised as a concern.1 This issue persists, with the 2024 Health of the Nation report identifying 69% of GPs noting they were experiencing burnout.2 In this longitudinal series in AJGP on doctors’ health and wellbeing, two research studies explored the factors either enhancing or detracting from GP registrars’ and supervisors’ wellbeing.3,4 A core theme evident within both studies is the centrality of meaningfulness. The meaning these groups could draw from activities across their personal and professional lives seemed a key determinant as to whether they thrived or experienced burnout. This article integrates these findings with the broader literature to examine this mechanism of meaningfulness and offers a conceptual model to practically apply this notion.
Meaningfulness
The literature supports an intuitive notion – that when GPs do what matters to them, they are more well. When doctors spend less time involved in patient care or have minimal diversity in their work, their wellbeing suffers.5–7 Conversely, when doctors can draw meaning from their work – whether that be through personal growth or connecting with others – they report greater wellbeing and lower distress.8–11 In a landmark study,12 doctors who spent a day a week engaged in the activities they found most meaningful in their job halved their odds of experiencing burnout.13 This finding has been replicated with Australian GPs who had diversified employment.14
Yet, defining ‘meaningfulness’ can be difficult. One way of making this more practical is through the lens of values. Fundamentally, values are the principles or ways of being that are important to a person, such as curiosity, justice or productivity. Importantly, research suggests that values are also key for doctors’ wellbeing. One study found that the degree to which Australian GPs’ values were fulfilled predicted whether they experienced burnout or were thriving.15 This aligns with previous suggestions that an incongruence between doctors’ and their workplace’s values can lead to burnout.3 Collectively, such evidence suggests that meaningfulness (specifically in the form of value fulfilment) might be a core mechanism for determining GPs’ wellbeing.16
A conceptual model
The importance of meaningfulness for GP wellbeing might be empirically supported, but it is somewhat abstract even with reference to values. Accordingly, a more pragmatic conceptual model is called for. The model proposed in this article builds upon the well-regarded Job Demands–Resources (JD-R) model.17 According to the JD-R model, burnout arises when the demands an employee faces exceed the resources they have to address the demands. The model proposed in this paper offers a more nuanced consideration of this process, with stronger reference to meaningfulness and wellbeing, and clearer application for individual GPs and practices to consider stressors and how to mitigate these (Figure 1). The model will be described, followed by a worked example to illustrate its application.
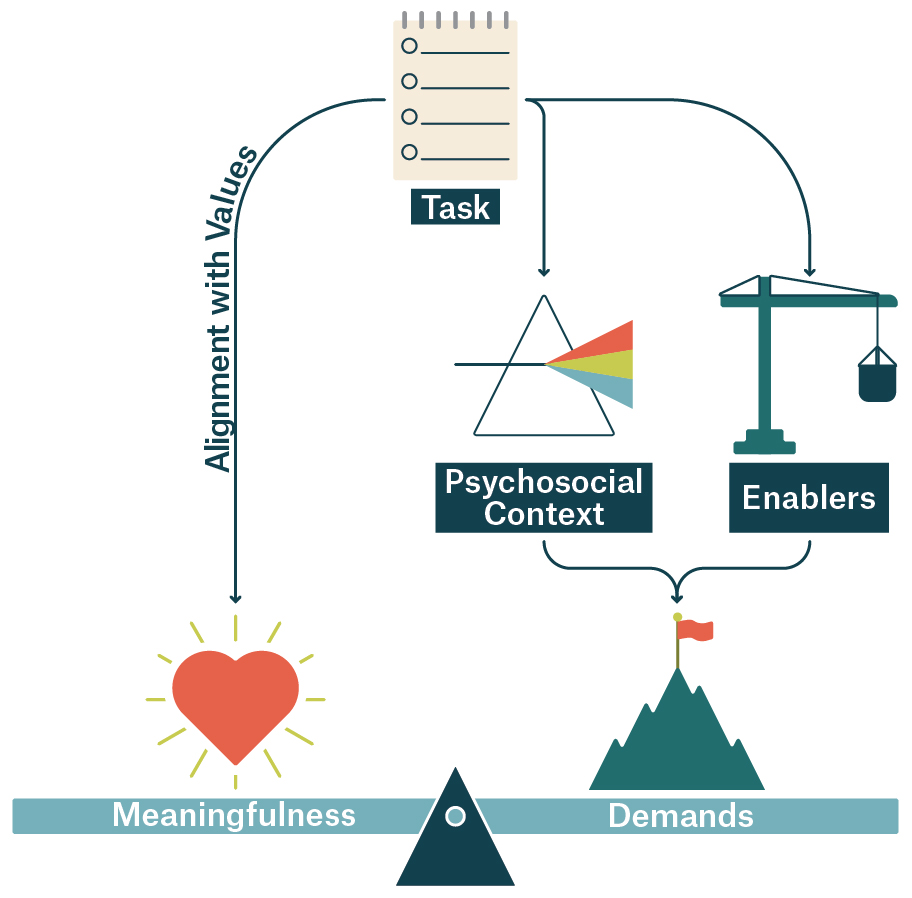
Figure 1. A conceptual model of how tasks influence general practitioners’ wellbeing.
Under this model, any task can be viewed as simultaneously having two components. The first is the meaning a GP can draw from the task. This is relatively simple, comprising which of a GP’s values that the task aligns with. Counterbalancing this is the demanding aspects of the task, which are the ways in which the task requires the GP to expend effort. This involves the physical, cognitive and emotional toll of the task. The novel aspect of the current model being presented concerns how these demands are further processed by the individual and the enablers around them.
Starting with the enablers, these are any factors external to an individual that can reduce how onerous a demand is. The impact of an enabler ranges from making a task simpler (eg reducing the number of questions in a form) through to eliminating the demands altogether (ie by delegating). As such, enablers can span a variety of levels, such as being able to delegate tasks to administrative staff in a practice, or systemic changes to consolidate paperwork requirements for patients to access services.
The other element is how the psychosocial context can minimise or magnify a task’s demandingness. Such factors include micro-level (eg an individual’s psychological personality traits), meso-level (eg practice culture) and macro-level (eg workforce shortages, medical culture). Critically, these factors might not directly relate to the specific demand itself, but serve as a lens to distort (favourably or unfavourably) how taxing the task is. The model proposes that a task’s inherent demands are then filtered through enablers (which minimise demands) and the context (which might increase or decrease demands), leading to a final level of ‘demandingness’ in a task. The balance between the task’s demandingness and meaningfulness ultimately determines whether the task is draining or replenishing for a GP. The accumulation of all the tasks that a GP faces and how meaningful or demanding they are perceived determines whether a GP’s wellbeing moves towards burnout or thriving.
Applying the model
To illustrate the practical use of the model, consider the following scenario. Suppose a GP needs to complete extensive paperwork to secure service funding for a patient. The impact of this task on the GP’s wellbeing can be explored through the four factors mentioned. The demands of the task are fixed: suppose the form will take an hour to complete, which includes searching through practice records for patient details, writing an opinion about the patient’s current and likely ongoing needs, and collating documentation from other health professionals to which the GP had referred the patient. The effort to complete these activities is what the task ‘costs’ the GP and, on their own, will diminish the GP’s wellbeing.
The remaining three factors can be considered to see the overall effect on the GP’s wellbeing. The first and simplest is enablers. Is it appropriate and feasible to delegate part of the task to someone else to complete? For example, the patient or their carer might be able to consolidate supporting documentation. Alternatively, this might be an appropriate task to delegate to someone else within the practice. At a broader system level, the funding body could streamline the forms to minimise the questions being asked. Building enablers at any of these points will reduce the overall ‘cost’ to the GP.
Second is considering the psychosocial context. One aspect could be experience – a GP who has filled out similar forms dozens of times before will know what to do and thus take considerably less time and effort than a GP who has never done this before. Psychologically, a GP who is already experiencing burnout might struggle to manage the cognitive load of the task, thus the task will take more time than for a GP who is otherwise well. If the GP is also a supervisor, they might find they have several interruptions during the process supporting their trainees and so it takes them extra time to gather their thoughts each time they resume the task. Suppose the practice culture prioritises financial income, this might mean the GP needs to do the task outside of business hours or feels pressured to rush through the task as quickly as they can. Each of these factors might magnify or minimise the inherent stress of the task itself, impacting the overall toll on the GP’s wellbeing.
Finally, one must consider how meaningful this task is for the GP. This can be done with reference to the GP’s values. For example, if this GP subscribes to values of caring, justice and contribution, this task of helping a patient receive the funding they need strongly fulfils those values. Accordingly, if the GP can recognise this alignment, the model proposes they will be replenished by this task. Conversely, if the GP more strongly subscribes to values of curiosity and creativity, this task might be less easily aligned with their values and so, on balance, it will have less of a replenishing effect for them.
Conclusion
As general practice continues to grapple with the issue of burnout, there is a growing need for solutions. A tangible approach appears to be building GPs’ sense of professional meaning. Fundamentally, reshaping systems and resourcing GPs so they can more strongly reconnect with meaningfulness will have a myriad of benefits for the profession. The model proposed within this paper offers guidance to this end, particularly for GPs and their practices. This paper highlights the vital importance of meaningfulness when visualising and investing in change. Finding opportunities to minimise demands and maximise meaning within everyday tasks might represent a key approach for building wellbeing and ensuring a sustainable career.
Key points
- Enhancing meaningfulness is a core wellbeing strategy for doctors.
- Meaningfulness can be considered in terms of values – ways of being that individuals see as intrinsically important.
- Tasks comprise both the demands that require exertion and the rewarding aspects (ie how they are meaningful).
- Tasks should be streamlined wherever possible with appropriate assistance provided to GPs to minimise the drains.
- GPs operate within a complex psychosocial context, which can influence the demands of a task.