Medical regulators seek to protect the public by investigating concerns that a doctor may be placing the public at risk of harm because of poor performance, conduct or health. The Australian Health Practitioner Regulation Agency (Ahpra) regulates medical doctors under Australia’s National Registration and Accreditation Scheme.1 Anyone can make a voluntary notification to Ahpra. Employers and health practitioners have a mandatory duty to report doctors who are practising while intoxicated by alcohol or drugs, or who are practising with a health impairment that places the public at risk of substantial harm.2 Following initial assessment, notifications are referred to the Medical Board of Australia for regulatory decisions.
Being the subject of a notification to Ahpra is often a distressing event for any doctor.3,4 Both Ahpra and the medical profession support efforts to reduce the stress and distress associated with notifications while still protecting the public.5 While vexatious notifications are relatively rare, a recent national ombudsman review recommended greater consistency and transparency to strengthen Ahpra’s approach to identifying notifications intended to cause harm.6 A deeper understanding of notifications may inform improvements in medical regulation, practitioner wellbeing and patient care.7,8
We analysed 10 years of de-identified Ahpra notifications from across Australia (excluding New South Wales [NSW]) linked with demographic data from the medical register. This study focuses on general practitioners (GPs), who are the largest medical specialty.9 GPs play a critical part in preventive and chronic disease care.10 However, they face increasing workloads, administrative burdens, workforce shortages and financial pressures.11,12 Stress and burnout among GPs are therefore increasing and may adversely affect patient care, as shown in prior studies of burnout in doctors.13,14
We describe the frequency, characteristics and outcomes of notifications, focusing on health-related concerns, and calculate multivariate odds of receiving a notification. The aim of this study was to identify demographic patterns associated with notifications, providing insights that may inform policy discussions and professional support strategies to mitigate the risk of notifications, support GP wellbeing and protect patient safety.
Methods
Study design
We conducted a retrospective cohort study using de-identified administrative data collected by Ahpra. Notifications about GPs registered between July 2012 and June 2022 were linked to demographic data from the medical register using unique identifiers. Focusing on health-related notifications, we described the source, nature and outcome of notifications. We used multivariate analyses to assess factors associated with increased odds of a notification.
Inclusion criteria
Our study included all specialist GPs registered during the study period. Registrations from NSW were excluded because of the state’s co-regulatory framework where notifications are managed separately. While Queensland also operates a co-regulatory model, health- related notifications are usually dealt with by Ahpra and the Medical Board of Australia, so sufficient notifications data were collected by Ahpra for inclusion in this study.4
Variables
GPs were grouped into 10-year age cohorts, adjusting over time. Country of initial medical qualification was categorised into three groups: Australia, comparable jurisdictions, and non-comparable jurisdictions. These categories were based on Ahpra’s Competent Authority pathway to registration, whereby New Zealand, UK, Republic of Ireland, USA and Canada are designated as having comparable medical training to Australia.15 Practice location was classified as metropolitan, regional, rural and remote, adapted from the Modified Monash Model.16
Ahpra classified notification sources into 25 categories, including ‘unclassified’ and ‘unknown’. These were recoded into six analytically meaningful groups. Notifications from patients, relatives or community members were coded as ‘member of the public’, whereas those from government entities (eg police) or anonymous notifications were coded as ‘other’. Notifications from ‘hospitals’, ‘education providers’ and ‘employers’ were collapsed into the broader category ‘employer’. Outcomes were coded as ‘no further action’, ‘non-restrictive sanctions’ (eg cautions), ‘conditions on practice’ or ‘removed from practice’ (suspension or cancellation). Importantly, no further action does not necessarily mean the concern was unsubstantiated, only that regulatory action was not required to protect the public.
Notifications were categorised into three streams: conduct, performance or health. Health concerns were further divided into mental health, substance use, physical health and cognitive impairment. We combined Ahpra’s data on ‘Alcohol – misuse, abuse or addiction’ and ‘Drugs – misuse, abuse or addiction’ into a single variable representing substance use. Some notifications raised multiple concerns across health, performance and conduct issues.
Analysis
Descriptive statistics summarise baseline GP characteristics and notification patterns. Baseline years were assigned as follows: the first year of registration as a specialist GP during the study period for GPs without notifications, and the year of the first notification for GPs with at least one notification. Multivariate logistic regression was used to assess the association between GP characteristics and the odds of a notification. Multinomial logistic regression examined the association between stream, source, nature and outcome of notifications. A sensitivity analysis focused only on notifications that resulted in regulatory action.
Analyses were performed using Stata 18.0 (StataCorp, College Station, TX, USA). The University of Melbourne’s Human Ethics Sub-Committee approved the study (HREC 22933).
Results
Sample characteristics
The dataset comprised 28,159 medical practitioners registered in Australia as specialist GPs from July 2012 to June 2022, with a median registration duration of 8 years (range 1–10 years). The proportion of GPs aged ≥70 years increased by over 40%, rising from 6.3% to 8.9% during the study period (Appendix 1; available online only).
Over the 10 years, Ahpra received 15,543 notifications regarding 8231 GPs, accounting for over 40% of notifications about medical doctors.
Approximately half (53.7%) of GPs were male, but they accounted for over two-thirds (68.4%) of notifications (Table 1). GPs aged ≥50 years of age constituted 43.8% of the workforce but received over 60% of notifications. GPs trained in non-comparable jurisdictions represented 25.7% of the workforce but accounted for 33.9% of notifications. All differences were significant (P <0.001). Notification numbers rose annually, driven by performance-related notifications (Figure 1).
|
Table 1. Characteristics at baseline of general practitioners (GPs) in Australia registered 2012–22A
|
|
Characteristics
|
GPs without complaints n (%)
|
GPs with complaints n (%)
|
P-valueB
|
|
Total
|
19,928
|
(70.8%)
|
8231
|
(29.2%)
|
|
|
Sex
|
<0.001
|
|
Male
|
9495
|
(47.6%)
|
5631
|
(68.4%)
|
|
|
Female
|
10,433
|
(52.4%)
|
2600
|
(31.6%)
|
|
|
Age group
|
<0.001
|
|
<30 years
|
294
|
(1.5%)
|
15
|
(0.2%)
|
|
|
30–39 years
|
6654
|
(33.4%)
|
942
|
(11.4%)
|
|
|
40–49 years
|
5724
|
(28.7%)
|
2211
|
(26.9%)
|
|
|
50–59 years
|
4259
|
(21.4%)
|
2529
|
(30.7%)
|
|
|
60–69 years
|
2285
|
(11.5%)
|
1849
|
(22.5%)
|
|
|
≥70 years
|
712
|
(3.6%)
|
685
|
(8.3%)
|
|
|
Qualification country
|
<0.001
|
|
Australia
|
12,544
|
(66.1%)
|
4443
|
(56.5%)
|
|
|
Comparable jurisdictions
|
2221
|
(11.7%)
|
753
|
(9.6%)
|
|
|
Non-comparable jurisdictions
|
4222
|
(22.2%)
|
2665
|
(33.9%)
|
|
|
Remoteness of practice
|
<0.001
|
|
Metropolitan
|
13,102
|
(68.1%)
|
5964
|
(73.1%)
|
|
|
Regional
|
2597
|
(13.5%)
|
893
|
(10.9%)
|
|
|
Rural
|
2885
|
(15.0%)
|
1135
|
(13.9%)
|
|
|
Remote
|
663
|
(3.4%)
|
168
|
(2.1%)
|
|
|
Note: n = 1311 (4.7%) missing data for country of qualification and n = 752 (2.7%) missing data for remoteness.
A Registrations from New South Wales GPs excluded.
B P-values based on Chi-squared test comparing characteristics of GPs with and without complaints.
|
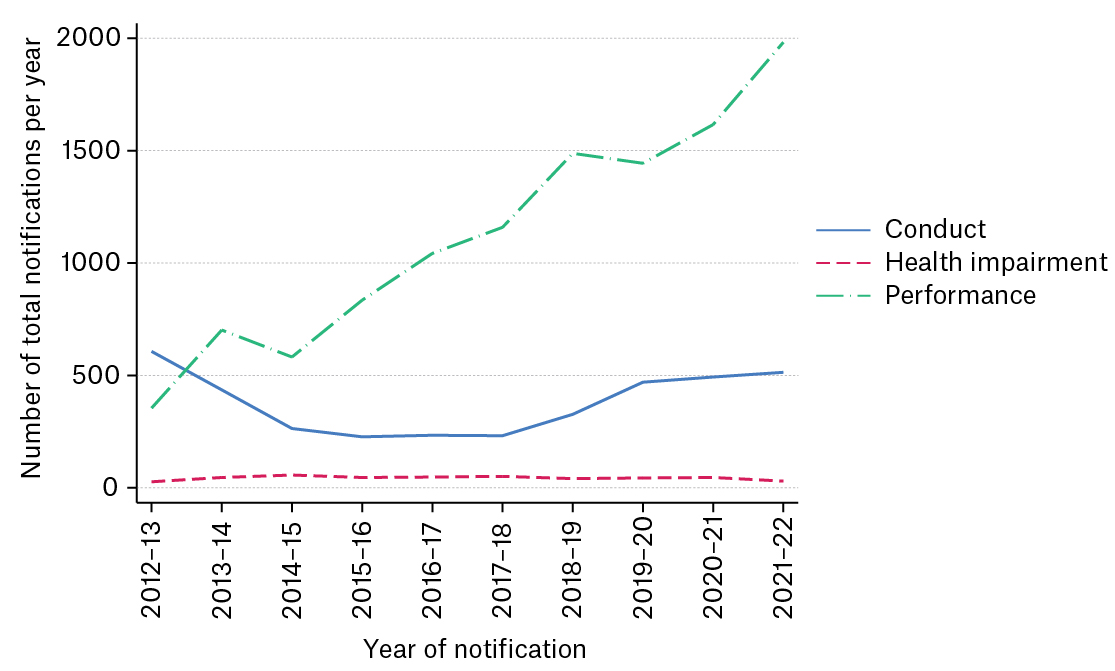
Figure 1. Trends in conduct, performance and health-related notifications about general practitioners received by the Australian Health Practitioner Regulation Agency (2012–22).
Risk factors
In multivariate analysis (Table 2), male GPs had nearly twice the odds of receiving a notification when compared with female GPs (odds ratio [OR]: 1.95, 95% confidence interval [CI]: 1.84–2.07). The odds of a notification increased monotonically with age, with GPs aged ≥70 years having nearly seven-fold higher odds when compared with those aged 30–39 years (OR: 6.96, 95% CI: 6.04–8.02). A sensitivity analysis (Appendix 2; available online only) focusing only on notifications that led to regulatory action found that the association with age ≥70 years strengthened further (OR: 10.38, 95% CI: 8.65–12.45).
|
Table 2. Odds of receiving a notification to Ahpra by general practitioner characteristics
|
|
Characteristics
|
Multivariate logistic regression analysis
|
|
|
Odds ratio
|
95% CI
|
P-value
|
|
Sex
|
|
Male
|
1.95
|
1.84–2.07
|
<0.001
|
|
Female
|
1.00
|
|
|
|
Age group
|
|
<30 years
|
0.42
|
0.25–0.72
|
0.001
|
|
30–39 years
|
1.00
|
|
|
|
40–49 years
|
2.39
|
2.19–2.60
|
<0.001
|
|
50–59 years
|
3.81
|
3.49–4.16
|
<0.001
|
|
60–69 years
|
5.41
|
4.91–5.96
|
<0.001
|
|
≥70 years
|
6.96
|
6.04–8.02
|
<0.001
|
|
Qualification country
|
|
Australia
|
1.00
|
|
|
|
Comparable jurisdictions
|
1.05
|
0.95–1.15
|
0.336
|
|
Non-comparable jurisdictions
|
1.89
|
1.77–2.01
|
<0.001
|
|
Remoteness of practice
|
|
Metropolitan
|
1.00
|
|
|
|
Regional
|
0.80
|
0.74–0.88
|
<0.001
|
|
Rural
|
0.90
|
0.83–0.97
|
0.008
|
|
Remote
|
0.63
|
0.52–0.75
|
<0.001
|
|
Ahpra, Australian Health Practitioner Regulation Agency; CI, confidence interval; OR, odds ratio.
|
GPs with initial medical qualifications from non-comparable jurisdictions had higher odds of notifications (OR: 1.89, 95% CI: 1.77–2.01) than those trained in Australia. GPs from comparable jurisdictions had similar odds (OR: 1.05, 95% CI: 0.95–1.15) to Australian-trained GPs. When compared with metropolitan GPs, the odds of a notification were lower for those in regional (OR: 0.80, 95% CI: 0.74–0.88) and remote (OR: 0.63, 95% CI: 0.52–0.75) areas.
Notification characteristics
Notification characteristics are shown in Table 3. Notifications related to performance (11,206/15,543, 72.1%), conduct (3804/15,543, 24.6%) and health (436/15,543, 2.8%). Performance-related notifications spiked from under 500 in 2012 to nearly 2000 in 2022, whereas conduct and health-related notifications remained steady across the study period (Figure 1).
|
Table 3. Characteristics of notifications by streamA
|
|
Notification characteristics
|
Health
impairment
n (%)
|
Conduct
n (%)
|
Performance
n (%)
|
Chi-squared P-value
|
|
Total
|
436
|
(2.8%)
|
3804
|
(24.6%)
|
11,206
|
(72.5%)
|
|
|
Source of complaint
|
<0.001
|
|
Member of the public
|
88
|
(20.2%)
|
2522
|
(66.3%)
|
9282
|
(82.8%)
|
|
|
Employer
|
39
|
(8.9%)
|
124
|
(3.3%)
|
156
|
(1.4%)
|
|
|
Treating practitioner
|
46
|
(10.6%)
|
15
|
(0.4%)
|
15
|
(0.1%)
|
|
|
Other practitioner
|
123
|
(28.2%)
|
463
|
(12.2%)
|
665
|
(5.9%)
|
|
|
Self
|
53
|
(12.2%)
|
51
|
(1.3%)
|
30
|
(0.3%)
|
|
|
Other
|
87
|
(20.0%)
|
629
|
(16.5%)
|
1058
|
(9.4%)
|
|
|
Type of notification
|
<0.001
|
|
Mandatory
|
131
|
(30.0%)
|
286
|
(7.5%)
|
385
|
(3.4%)
|
|
|
Not mandatory
|
305
|
(70.0%)
|
3518
|
(92.5%)
|
10,821
|
(96.6%)
|
|
|
Outcome of notification
|
<0.001
|
|
No further action
|
266
|
(61.3%)
|
2626
|
(70.0%)
|
7718
|
(69.1%)
|
|
|
Referral to another body
|
4
|
(0.9%)
|
430
|
(11.5%)
|
1791
|
(16.0%)
|
|
|
Voluntary undertaking
|
60
|
(13.8%)
|
45
|
(1.2%)
|
175
|
(1.6%)
|
|
|
Non-restrictive sanctions
|
22
|
(5.1%)
|
352
|
(9.4%)
|
724
|
(6.5%)
|
|
|
Conditions on practice
|
75
|
(17.3%)
|
243
|
(6.5%)
|
723
|
(6.5%)
|
|
|
Removed from practice
|
7
|
(1.6%)
|
56
|
(1.5%)
|
39
|
(0.3%)
|
|
|
A Counts and percentages based on non-missing data (stream was unknown for n = 97 notifications).
|
Notifications from patients and other members of the public were predominantly performance related (82.8%). Over a third (38.8%) of health-related concerns were raised by another health practitioner. Multinomial analysis (Appendix 3; available online only) revealed that, compared with conduct and performance concerns, health- related concerns were more likely to be raised by treating practitioners (relative risk ratio [RRR] = 120.44, 95% CI: 69.11–209.91) or the GPs themselves (RRR = 69.99, 95% CI: 45.47–107.73). The absolute number of health impairment notifications about GPs identified as coming from treating practitioners was small, with only 46 such reports across 10 years. Although the majority (94.8%) of total notifications were voluntary, 30% of health-related notifications were mandatory.
Notification outcomes
Nearly 70% of all notifications resulted in no regulatory action, 14.5% in referral to another body, 7.2% in non-restrictive sanctions and 1.8% in a voluntary undertaking by the doctor. Few (0.7%) led to registration cancellation, and 54.9% of these were conduct-related concerns. Health- related notifications more frequently led to conditions on practice (17.3%), compared with conduct (6.5%) and performance- related (6.5%) concerns. These differences were statistically significant (Chi-squared P <0.001).
Health-related notifications
Health-related notifications are presented in Table 4. Mental health concerns (37.9%) and substance use concerns (31.8%) were most common, followed by cognitive impairment (24.7%) and physical impairment (5.5%). Male GPs were overrepresented across all health concerns. Among health- related notifications for female GPs, mental health was the most common concern. Substance use, including alcohol use, was the most common issue among rural GPs, whereas cognitive concerns prevailed among older GPs.
|
Table 4. Distribution of specific concerns raised in health impairment notifications 2012–22A
|
|
Characteristics
|
Mental health
n (%)
|
Substance use
n (%)
|
Cognitive impairment
n (%)
|
Physical impairment
n (%)
|
Chi-squared P-value
|
|
Total
|
192
|
(37.9%)
|
161
|
(31.8%)
|
125
|
(24.7%)
|
28
|
(5.5%)
|
|
|
Sex
|
<0.001
|
|
Male
|
115
|
(59.9%)
|
116
|
(72.0%)
|
104
|
(83.2%)
|
22
|
(78.6%)
|
|
|
Female
|
77
|
(40.1%)
|
45
|
(28.0%)
|
21
|
(16.8%)
|
6
|
(21.4%)
|
|
|
Age group
|
<0.001
|
|
30–39 years
|
17
|
(8.9%)
|
15
|
(9.3%)
|
2
|
(1.6%)
|
1
|
(3.6%)
|
|
|
40–49 years
|
49
|
(25.5%)
|
37
|
(23.0%)
|
6
|
(4.8%)
|
5
|
(17.9%)
|
|
|
50–59 years
|
72
|
(37.5%)
|
70
|
(43.5%)
|
26
|
(20.8%)
|
7
|
(25.0%)
|
|
|
60–69 years
|
37
|
(19.3%)
|
29
|
(18.0%)
|
31
|
(24.8%)
|
10
|
(35.7%)
|
|
|
≥70 years
|
17
|
(8.9%)
|
10
|
(6.2%)
|
60
|
(48.0%)
|
5
|
(17.9%)
|
|
|
Qualification country
|
<0.001
|
|
Australia
|
132
|
(72.5%)
|
103
|
(68.2%)
|
62
|
(62.6%)
|
16
|
(72.7%)
|
|
|
Comparable jurisdictions
|
21
|
(11.5%)
|
28
|
(18.5%)
|
12
|
(12.1%)
|
3
|
(13.6%)
|
|
|
Non-comparable jurisdictions
|
29
|
(15.9%)
|
20
|
(13.2%)
|
25
|
(25.3%)
|
3
|
(13.6%)
|
|
|
Remoteness of practice
|
<0.001
|
|
Metropolitan
|
150
|
(78.5%)
|
97
|
(61.0%)
|
89
|
(71.2%)
|
19
|
(67.9%)
|
|
|
Regional
|
17
|
(8.9%)
|
13
|
(8.2%)
|
20
|
(16.0%)
|
5
|
(17.9%)
|
|
|
Rural
|
19
|
(9.9%)
|
34
|
(21.4%)
|
13
|
(10.4%)
|
4
|
(14.3%)
|
|
|
Remote
|
5
|
(2.6%)
|
15
|
(9.4%)
|
3
|
(2.4%)
|
0
|
(0.0%)
|
|
|
A Excludes n = 53 health-related notifications without a health issue specified.
|
Discussion
This large cohort study found that GPs carry a high burden of notifications, accounting for approximately 40% of notifications about medical doctors over 10 years. In addition to any true differences in notification propensity, this likely reflects their central role in patient care, as well as the inherently higher consultation volumes in GP practice.17 Although most notifications resulted in no further regulatory action, the process is nevertheless stressful and can adversely affect a doctor’s wellbeing.2,3
Further research is needed to understand the increase in performance-related notifications. Relevant factors during the study period may include the COVID-19 pandemic, which disrupted access to and continuity of care; increased use of telehealth;18 and health workforce shortages.11
Health-related notifications were uncommon, accounting for fewer than 3% of notifications. Health-related notifications were more likely to result in conditions being placed on a GP’s practice when compared with conduct or performance concerns. Although most notifications came from patients or the public, health-related notifications more frequently came from treating practitioners or colleagues or through GPs self-notifying. This finding is likely to reflect practitioners having greater health literacy, and more opportunities to identify health-related concerns, compared with patients, who are more likely to focus on a doctor’s performance and conduct. Given the well-known barriers doctors face in seeking healthcare,19 ongoing work is needed to ensure that fear of mandatory reporting does not deter GPs from seeking care. This includes supporting treating practitioners in managing GPs with health impairments and ensuring that GPs and employers correctly understand the high threshold for mandatory reporting.
Our finding that male GPs had higher odds of receiving a notification than female GPs aligns with previous studies of complaints against health professionals.20,21 Although we could not control for working hours, prior research shows that the elevated medicolegal risk among male doctors persists even after controlling for this.21 The overrepresentation of male GPs across health-related concerns aligns with studies showing that men are less likely to seek help for health problems22 and more likely to engage in risk-taking behaviour.23
Our finding that older GPs have higher odds of a notification than younger peers is also consistent with previous research.21 Older GPs may face challenges in adapting to new standards of care, burnout after years of service and their own age-related health issues.24–26 In August 2024, the Medical Board of Australia proposed mandatory health checks for all doctors aged over 70 years.27 However, this proposal was controversial within the profession,28 and in December 2025, the Medical Board of Australia opted for profession-led support for late-career doctors instead.29 We found that the proportion of GPs aged ≥70 years increased from 6.3% to 8.9% during the study period. Policies targeting older GPs should consider not only the risk of cognitive decline for patient care, but also the potential workforce consequences if older GPs retire prematurely.
The underrepresentation of remote GPs in notifications data may reflect the complexities in healthcare access and use by people in remote communities, such as closer therapeutic relationships,30 or possible barriers faced by patients in raising concerns about a GP in an already underserviced area.31 Substance use, including alcohol use, was the most frequently reported health- related concern among rural and remote GPs. In Australia and internationally, risky alcohol consumption is more common in remote communities when compared with urban areas.32,33 These findings support initiatives to improve the health of rural and remote GPs, such as the Rural Doctors Foundation, which delivers GP services to rural and remote health practitioners through its GPs4RuralDocs program.34
The extent to which notification patterns reflect GP characteristics versus factors at a systems level is unclear. For example, GPs with initial medical qualifications from non-comparable jurisdictions had nearly double the odds of a notification when compared with those who trained in Australia. Furthermore, these doctors were underrepresented in health-related notifications. This finding may reflect systemic problems such as limited institutional support in induction, supervision, registration and accreditation processes for international medical graduates, as identified in the 2012 ‘Lost in the labyrinth’ report.35 This may also raise questions about whether unconscious bias among notifiers, communication challenges, or stigma regarding mental illness may lead to some concerns about GPs from non-comparable jurisdictions being misattributed to poor performance or misconduct rather than recognised as health related.
Strengths and limitations
This study is the first internationally to analyse a longitudinal dataset of notifications about GPs to a national health practitioner regulator. The comprehensive nature of the data, encompassing all GPs from seven states and territories over a 10-year period, and the availability of denominator data yielded robust findings.
We note that notifications are an imperfect measure of health impairments and other risks to the public. Not all concerns are notified to Ahpra, and some of the concerns raised in notifications may not be substantiated.6 Furthermore, this analysis is limited to notifications per GP rather than per consultation, which should be taken into consideration when comparing the number of notifications about GPs relative to the rest of the medical workforce, given that GPs have higher patient exposure.
The exclusion of NSW registrations and the lack of data on GPs’ working hours or patient volumes are important limitations. Future research could incorporate time-varying models to assess changes in risk of notification over time.
Conclusions
Being the subject of an Ahpra notification can be stressful for any GP, yet it is a relatively common event. Notifications are unevenly distributed, with male, metropolitan and older GPs, as well as those trained in non-comparable jurisdictions, having higher odds of a notification. Notification patterns should be interpreted in light of both provider and system-level influences.
Health-related notifications, though uncommon, tend to have more serious regulatory consequences than conduct or performance concerns. There may be opportunities for early identification and intervention to support the overall health of male GPs, the mental health of female GPs, substance use among remote GPs and cognitive impairment in older GPs. Any such interventions by policymakers and the profession should aim to support GPs while also seeking to protect patients from harm. There is an ongoing need to reduce barriers to doctors’ help-seeking and address the broader factors contributing to health- related notifications.