Residual risk of atherosclerotic cardiovascular disease (ASCVD) generally refers to the risk of an event such as an acute coronary syndrome (ACS), stroke or symptomatic peripheral arterial disease that remains after addressing known and modifiable risk factors. These include hypertension, hypercholesterolaemia, diabetes mellitus, smoking, an adverse diet and sedentary behaviour. Other components of residual risk not traditionally deemed to be modifiable include lipoprotein(a) (Lp(a)), inflammation, male sex and advancing age. For some of these, the landscape is changing. For example, certain anti-inflammatory medications have been experimentally shown to reduce the risk of further cardiovascular events in patients with established cardiovascular disease.1,2 Lp(a) is predominantly genetically determined, and plasma concentrations associated with increased cardiovascular risk are found in one in five people.3 There is growing recognition that the risk associated with Lp(a) can, and should, be modified with aggressive lipid-lowering and other strategies, even if lowering the concentration of Lp(a) itself is not yet readily achievable.3–5 However, in the near future, therapeutic agents that directly lower Lp(a) concentrations, and are currently the subject of major clinical trials, could address the residual risk wrought by Lp(a).
Objective
To outline the clinical importance and detection of, and the current and future management of, elevated Lp(a).
Discussion
What is Lp(a)?
First discovered more than 6 decades ago,6 Lp(a) is of similar size and composition to low-density lipoprotein (LDL), with the key difference of an additional component called apolipoprotein(a), which is bound to apolipoprotein-B100 (apoB-100) common to both particles (Figure 1).7 Despite similar structures, the production and clearance pathways of Lp(a) and LDL differ.8 This has important implications for treatment: whereas statins increase the clearance of LDL particles by upregulating the LDL receptors on liver cells (secondarily decreasing cholesterol production), this does not appear to be a major pathway for the degradation for Lp(a) particles,9 making statins ineffective in lowering Lp(a) concentrations specifically. Nonetheless, statins and other LDL cholesterol-lowering therapies have an important role in reducing the risk associated with Lp(a), as will be discussed later.
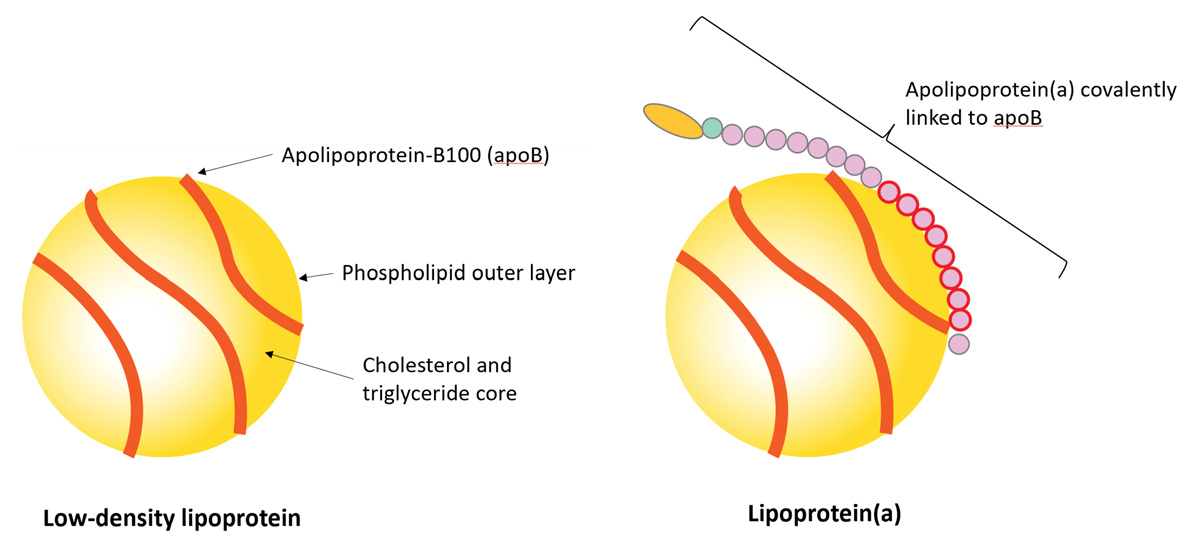
Figure 1. Structures of low-density lipoprotein and lipoprotein(a).
Low-density lipoprotein (LDL) and lipoprotein(a) (Lp(a)) are of similar structure, each being spherical particles with cholesterol and triglycerides surrounded by a phospholipid layer, and each with the structural apolipoprotein-B100 protein, which in the case of LDL also acts as its binding site for the LDL receptor, which clears it from the circulation. Lp(a) has an additional component, apolipoprotein(a), which might impart additional prothrombotic qualities.
Clinical importance of Lp(a)
Once considered a particle of uncertain significance, Lp(a) has more recently been firmly established as a causal risk factor for coronary artery disease, stroke, peripheral arterial disease and calcific aortic valve stenosis.3 With its plasma concentrations strongly determined by variation in the LPA gene, epidemiological methods have been employed to correlate the genetic predisposition to elevated Lp(a) concentrations from birth with the development of ASCVD later in life, favouring causality of ASCVD attributable to Lp(a).10 The structural similarity of Lp(a) with LDL particles and its preferential carriage of inflammatory oxidised phospholipids provides a strong mechanistic basis for its atherogenicity, and Lp(a) might have additional, unique prothrombotic characteristics.11,12 Indeed, a single Lp(a) particle is probably more atherogenic than a single LDL particle, although LDL particles are present at much higher concentrations.13
Around one in five people has an Lp(a) concentration above 100 nmol/L,14 which is commonly deemed to be an ASCVD risk cut-off. However, the relationship between Lp(a) concentrations and cardiovascular risk seems to be continuous across the concentration range, independently and additional to other risk factors including LDL-cholesterol. At very high concentrations of Lp(a) the risk of ASCVD might be multiplied four-fold or more, compared with low concentrations.15 Differences in the plasma concentrations of Lp(a) have been observed across ancestral groups; people of European ancestry tend to have higher concentrations than those of East Asian ancestry, whereas those of African American and South Asian ancestry have higher concentrations than Europeans.16 A study by Xiong et al suggests that in an Aboriginal population from Western Australia, Lp(a) concentrations might be similar to those of European ancestry.17 Data relating to Lp(a) levels in Aboriginal and Torres Strait Islander people are otherwise limited. There are no ancestry-specific recommendations relating to testing or managing Lp(a).
When to consider measuring Lp(a)
Guidelines from around the world differ in their recommended indications for testing Lp(a). However, all agree that testing is justified by the potential benefit of identifying a high concentration leading to the upgrading of a patient’s estimated ASCVD risk, and subsequent commencement of risk-reducing measures. Some (eg those published by the European Atherosclerosis Society) recommend that every adult should have their Lp(a) measured.5 The current Australian guideline published by the Australian Atherosclerosis Society (AAS) takes a more targeted approach (Table 1), suggesting testing those with a family history of elevated Lp(a) or young-onset ASCVD (which might unknowingly be due to elevated Lp(a)), or otherwise increased cardiovascular risk.3
|
Table 1. Recommendations on patient groups to consider for lipoprotein(a) testing3
|
|
Indication
|
Rationale
|
|
People at very high risk of ASCVD or with established ASCVD (prior myocardial infarction, stroke or peripheral arterial disease)
|
The finding of a high Lp(a) could lead to an intensification of risk-reducing measures such as the addition of a PCSK9 inhibitor, aspirin or apheresis, and to family member testing
|
|
People with a family history of premature ASCVD or of elevated Lp(a)
|
Lp(a) is strongly heritable, and a family history of ASCVD could reflect a genetic predisposition to elevated Lp(a)
|
|
People with premature or rapidly progressive aortic stenosis
|
Lp(a) is a strong risk factor for calcific aortic stenosis
|
|
People with a very high coronary artery calcium score, diabetes mellitus, familial hypercholesterolaemia or chronic kidney disease
|
The finding of a high Lp(a) in addition to these ASCVD risk factors is likely to lead to an intensification of risk-reducing measures
|
|
People in whom LDL-cholesterol lowering is less effective than expected despite good adherence to guideline-recommended doses of lipid-lowering therapy
|
Elevated Lp(a) can artefactually increase LDL-cholesterol concentrations but as it is not lowered by most existing lipid-lowering therapies, apparent LDL-cholesterol concentrations will not respond as expected
|
|
ASCVD, atherosclerotic cardiovascular disease; LDL, low-density lipoprotein; Lp(a), lipoprotein(a); PCSK9, proprotein convertase subtilisin/Kexin type 9.
|
Lp(a) typically only needs measuring once, especially if the concentration is low, given that it is not subject to significant variation with age, diet or currently available medications. Menopause can increase Lp(a) concentrations and while menopausal hormone therapy can modestly reduce Lp(a), it is not generally recommended as a specific treatment.3 Acute inflammation, including post-ACS, can transiently reduce Lp(a) concentrations.3 Fasting is not required for Lp(a) testing. While a Medicare rebate for Lp(a) testing is not currently available, the out-of-pocket cost to the patient is typically modest, particularly given that repeat testing is not generally required. Nonetheless, this might represent a barrier to testing, particularly in individuals from challenged socioeconomic backgrounds.
Risk classification in patients with elevated Lp(a)
An elevated Lp(a) increases the likelihood that a patient will experience future cardiovascular disease (CVD), but by how much? The Australian CVD Risk Calculator18 and many other similar tools do not yet incorporate Lp(a) as a variable. In general, the finding of elevated Lp(a) can be thought of as upgrading the classification of risk by at least one category – for instance, a person otherwise deemed to be at ‘intermediate’ (5–10%) 5-year CVD risk might be reclassified to ‘high’ (10–15%) 5-year CVD risk. Many ASCVD risk calculators are also limited as assessment and education tools for younger patients, given their limited 5- or 10- year horizons. A useful tool that addresses these issues can be found at lpaclinicalguidance.com, which is based on data from the UK Biobank and incorporates Lp(a) measurement along with other important risk factors, providing ASCVD risk estimates to the age of 80 years from any baseline age of 30 years or older.19
How should elevated Lp(a) be managed today?
Given that Lp(a)-lowering therapeutic agents are not yet readily accessible, current recommendations on the management of elevated Lp(a) centre on reducing ASCVD risk through other mechanisms. These entail diet and lifestyle factors, the close management of risk factors such as hypertension and diabetes mellitus, and assertive management of LDL-cholesterol (Table 2). Statins and ezetimibe do not reduce Lp(a) concentrations, but lowering LDL-cholesterol is expected to reduce the overall ASCVD risk heightened by elevated Lp(a). Proprotein convertase subtilisin/Kexin type 9 (PCSK9) inhibitors lower Lp(a) concentrations by around 20–30% as well as more substantially lowering LDL-cholesterol, and in some clinical trials demonstrated a stronger cardiovascular benefit in patients with higher baseline Lp(a) concentrations.20 While PCSK9 inhibitors do not carry a Pharmaceutical Benefits Scheme subsidy specific to elevated Lp(a) or to its lowering, they are an option in patients who are otherwise eligible to receive a subsidy (eg many patients with familial hypercholesterolaemia) or are able to self-fund their treatment. There is some evidence that aspirin could provide a cardiovascular benefit that outweighs its risks in the primary prevention setting for patients with increased Lp(a), but there is not yet a firm recommendation for implementing this into routine clinical practice.21
|
Table 2. Recommendations on the management of adults with elevated lipoprotein(a)3
|
|
Patient group
|
Recommendation
|
|
All patients with Lp(a) >100 nmol/L, including below categories
|
Address all modifiable risk factors such as diet, smoking, obesity, hypertension, renal impairment, diabetes and elevated LDL-cholesterol
|
|
Lp(a) >100 nmol/L and intermediate absolute ASCVD risk
|
Consider Lp(a) a risk-modifying factor that would prompt offering lipid-lowering therapy to reduce LDL-cholesterol
|
|
Lp(a) >100 nmol/L and high or very high absolute ASCVD risk
|
Consider more intensively lowering LDL-cholesterol below guideline-recommended targets using maximally tolerated statins, ezetimibe and PCSK9 inhibitors
|
|
Lp(a) >200 nmol/L and recurrent ASCVD events despite maximal lipid lowering therapy
|
Consider lipoprotein apheresis (a method of periodically filtering lipoproteins from the blood using a machine)
|
|
Lp(a) >100 nmol/L with evidence of subclinical ASCVD or multiple other ASCVD risk factors
|
Consider the use of aspirin for primary prevention if there are no contraindications (eg bleeding-related)
|
|
ASCVD, atherosclerotic cardiovascular disease; LDL, low-density lipoprotein; Lp(a), lipoprotein(a); PCSK9, proprotein convertase subtilisin/Kexin type 9.
|
How might elevated Lp(a) be treated in the future?
Several experimental Lp(a)-lowering medications have been shown to reduce plasma concentrations of Lp(a) by as much as 80–90%, but whether they reduce ASCVD risk is the subject of ongoing clinical trials. The most progressed of these trials regards pelacarsen, an antisense oligonucleotide. Pelacarsen is a strand of ribonucleic acid (RNA) that is complementary to the messenger RNA (mRNA) of apolipoprotein(a). Pelacarsen is able to bind to that mRNA and force its degradation before it can be translated into a protein, thereby preventing the formation of the Lp(a) particle.22 The results of the Phase III Lp(a)HORIZON secondary prevention study of pelacarsen are expected in late 2026.23 Other medications in clinical trials include olpasiran, which also uses a gene silencing approach, and muvalalpin which stops apolipoprotein(a) binding to apoB-100, therefore preventing the final assembly of the Lp(a) particle.24,25
Conclusion
Ample evidence and expert guidance support the routine measurement of Lp(a) as an actionable independent risk factor to improve the accuracy of ASCVD risk prediction and target risk-reducing therapy in today’s clinical setting. When available, Lp(a)-lowering medications could represent a new frontier in redefining Lp(a) as a directly treatable and modifiable entity, substantially addressing residual cardiovascular risk.
Key points
- Lp(a) is a similar particle to LDL and causes atherosclerosis and aortic valve stenosis.
- One in five people has Lp(a) levels elevated to a degree that is associated with increased CVD risk.
- Some guidelines recommend testing Lp(a) in every adult patient; others focus on patients with other risk factors such as diabetes mellitus, familial hypercholesterolaemia and an adverse family history of cardiovascular disease.
- Treatment of patients with elevated Lp(a) is by general risk-reducing measures, including LDL cholesterol-lowering therapy in some patients, even though these do not reduce Lp(a) concentrations.
- New Lp(a)-lowering therapies are under investigation, with results of the first cardiovascular outcomes-based trials imminently expected.