Attention deficit hyperactivity disorder (ADHD) is increasingly managed within general practice, supported by evolving shared-care models and expanded general practice training. For many clinicians, medication decisions are one of the most challenging aspects of ADHD care because of variability in response, tolerability and patient preference in real-world practice, as well as considerable jurisdictional variability in prescribing regulations.1–3
Medication can play an important part in improving day-to-day functioning in ADHD, but it does not replace the need for robust and evidence-based psychosocial supports and psychoeducation such as lifestyle modification and input from an experienced psychologist.1–3 Recent Australian data demonstrates increasing use of both stimulant and non-stimulant medications across the lifespan, reflecting changing models of care and prescribing patterns.4
Stimulants demonstrate the greatest effect sizes for core ADHD symptoms in meta-analyses, although individual response remains variable.5 In general practice, medication initiation and adjustment should typically occur over multiple reviews and involve shared decision-making, with a focus on functional outcomes rather than symptom scores alone. This is particularly important in the Australian context, where prescribing authority, co-management arrangements and models of care vary across jurisdictions.
GPs might encounter strong expectations around stimulant treatment, alongside concerns about adverse effects and long-term use. At the same time, some patients might be hesitant to use stimulant medications or might have clinical features that make alternative options more appropriate.
Response to treatment is heterogeneous, and uncertainties remain regarding long-term outcomes and optimal sequencing of therapies.5,6 While stimulants remain the recommended starting point for many patients, effective care relies on an individualised approach, with an expectation that medication trials and adjustments are often required.
When to initiate medication
In line with the evidence based Australasian ADHD Professionals Association (AADPA) Australian Evidence-Based Clinical Practice Guideline for ADHD and Prescribing Guide documents (together ‘ADHD Guidelines’), medication should be considered as one component of a multi-modal treatment plan when ADHD symptoms are contributing to significant functional impairment in areas including education, work, relationships or daily functioning.1 A formal diagnosis and assessment of impairment across settings are essential prerequisites.
For most school-aged children, adolescents and adults, medication should be considered alongside behavioural and psychosocial strategies as part of a broader management plan.1,2,7 Considerations might differ across the lifespan, including school-related functioning in children and occupational or executive functioning demands in adults. In younger children, medication might be considered in more severe cases where non-pharmacological strategies have not been sufficient.1
In general practice, the decision to initiate medication is rarely purely clinical and might also be shaped by jurisdiction-specific prescribing arrangements and shared-care requirements. Patient goals, concerns about medication, prior experiences and family perspectives all influence whether and when treatment is started. This threshold will vary between individuals and often depends on the degree of functional impairment rather than symptom severity alone. Framing medication as a tool to support functioning, rather than a way to eliminate ADHD symptoms entirely, can help align expectations early. Further, the careful management of comorbidities might be required prior to initiating medication, particularly stimulant medication.
Choosing an initial medication
ADHD medication is commonly divided into two categories: stimulants and non-stimulants. The stimulants available in Australia include methylphenidate in short-, intermediate- and long-acting forms and amphetamine-based medicines (dexamfetamine and lisdexamfetamine). Non-stimulant medications include atomoxetine, bupropion (typically used under non-GP specialist guidance and hence not discussed here), guanfacine and clonidine. In rare cases, modafinil is considered an option.1,2,7
The ADHD Guidelines recommend stimulants as first-line treatment for most patients because of their strong efficacy.1,2 In practice, both stimulant and non-stimulant options might have a role in initial treatment decisions, depending on the individual clinical context.5,7,8 Stimulants are typically preferred where rapid symptom improvement is required (Table 1), allowing flexibility in duration of effect. Most patients will respond to at least one stimulant, although the optimal choice and dose cannot be predicted in advance.2 Consideration should also be given to possible medication diversion which should be part of the pre-initiation discussion with the patient.
Table 1. Schedule 8 psychostimulants used for ADHD treatment
|
Drug
|
Brands
|
Duration of action (hours)
|
Suggested max daily dose (mg)
|
Doses/day
|
Comments
|
|
Lisdexamfetamine
|
Vyvanse
|
10–13
|
70
|
1
|
Take before 9 am
|
|
Dexamfetamine
|
Generic only
|
4
|
40
|
2 or 3
|
Last dose before 4 pm
|
|
Methylphenidate
(immediate release)
|
Ritalin
|
4 (short)
|
60
|
2 or 3
|
Last dose before 4 pm
|
|
Methylphenidate
(slow release)
|
Ritalin LA
Concerta
|
8 (intermediate)
12 (long)
|
72
|
1
|
|
Practice point: Check before you prescribe
The ADHD Guidelines provide a list of absolute and relative contraindications to the use of certain medications, and which screening tests and physical examinations (eg BMI) should be considered prior to initiating medication.
Non-stimulant medications might be considered where stimulant therapy is unsuitable, not tolerated, not preferred or declined (Table 2).1,2,7 Atomoxetine is a common first choice when concentration and attention issues are the primary concern. It is taken daily, requires gradual titration, and has a slower onset of benefit over several weeks.2,7
|
Table 2. Non-stimulant medications used for ADHD treatment
|
|
Drug
|
Duration of action
|
Dosing: Monotherapy
|
Doses/day
|
Comments
|
|
Atomoxetine
|
Variable half-life: 5–20 hours
|
Start with 40 mg daily
Increase every 3 days according to response to target dose of 80 mg
Maximum 100 mg daily
|
1–2
|
Consider if stimulant intolerance, concern regarding misuse/diversion, or anxiety co-occurring
4–8-week trial required
|
|
Guanfacine
|
Half-life: 10–17 hours
|
Start 1 mg orally at bedtime
Review after 1 week for effect
Increase by 1 mg weekly until adequate response or maximum dose of 7 mg daily reached
|
1
|
Consider if emotional dysregulation, impulsivity, hyperarousal, sleep difficulties
Slower onset
Monitor BP and sedation; taper gradually if discontinuing
4–8-week trial required
|
|
Clonidine
|
6–12 hours
|
Start at 25–50 mcg
Increase by 50 mcg every 3 days
Maximum 300 mcg daily
|
1–2
|
Consider if sleep-onset difficulties, hyperarousal, aggression or behavioural dysregulation
More sedating; multiple daily doses might be required
Monitor BP; taper gradually if discontinuing high frequent doses
2–4-week trial required
|
|
Note: For paediatric dosing, please refer to AADPA Prescribing Guide.2
ADHD, attention deficit hyperactivity disorder; BP, blood pressure.
|
Two alpha-2 adrenergic agonists, clonidine and guanfacine, might be considered. They are commonly used for issues with sleep, behavioural dysregulation and hyperarousal; addition of clonidine often addresses issues with sleep latency and is considered more sedating but can have more prominent side effects including hypotensive episodes and requires dosing multiple times a day. Guanfacine, a longer acting medication, is more selective for alpha-2 receptors in the prefrontal cortex and might be better suited to targeting specific executive dysfunction issues like emotional regulation and impulsivity.2,7 Guanfacine, and sometimes clonidine, should generally be tapered gradually when discontinuing treatment to minimise the risk of rebound hypertension and other withdrawal effects.2 For Pharmaceutical Benefits Scheme (PBS) subsidisation, guanfacine and atomoxetine require an ADHD diagnosis prior to the age of 18 years.
In practice, medication choice should be guided by specific symptoms, comorbidities (particularly mental health comorbidities), tolerability, duration of symptom coverage required and patient preference. It is helpful to frame the initial prescription as a first trial, with the expectation that adjustment or switching might be required.
Titration and optimisation
Optimising ADHD medication focuses on identifying a dose that provides functional benefit while remaining acceptable in terms of adverse effects. This process often requires iterative adjustment and clinical judgement, rather than being a predictable or linear titration pathway.2
A practical approach is to start at a low dose and titrate gradually, usually at intervals of 1–2 weeks guided by clinical response rather than a predetermined target dose. Both stimulant and non-stimulant medications require structured titration and review, although their onset of action differs.2
At each step, the key questions are:
- Is there a noticeable improvement in day-to-day functioning?
- Is the patient still experiencing difficulties?
- Are adverse effects emerging, and are they manageable?
- Does the duration of effect match the patient’s needs?
Practice point: Key drug interactions
Many patients with ADHD present with comorbidities for which they might be taking other medication. A full guide to medication interaction is presented in the ADHD Guidelines.2
Regarding stimulants, initial medication might be long- or short-acting. There is no preferred approach, although several considerations will guide this (Table 3). Prescribers should refer to current Australian prescribing resources such as the ADHD Guidelines for exhaustive dosing and titration schedules.2 Commonly used protocols are provided in Figures 1 and 2; a paediatric protocol is provided in Table 4. It should be noted that there are no ‘typical’ patients and that the review schedule suggested must be tailored to each patient.
|
Table 3. Pros and cons of short- versus long-acting Schedule 8 psychostimulant medication
|
|
Consideration
|
Comment
|
|
Dose optimisation
|
SA medications can be easier to up titrate and check for effect
|
|
Checking accuracy of ADHD diagnosis
|
SA medications have quicker on/off effect
Enables more accurate assessment of typical ADHD symptoms
|
|
Management of side effects
|
SA medication side effects do not last as long but risks possible stronger ‘rebound’
|
|
Logistics and possible stigma
|
SA medications must be dosed throughout the day and often necessitate medication to be dosed at work or school
|
|
Cost
|
SA medications are typically cheaper even with PBS cover for long-acting formulation
Efficacy of SA methylphenidate is currently required for PBS subsidy of long-acting forms
|
|
ADHD, attention deficit hyperactivity disorder; PBS, Pharmaceutical Benefits Scheme; SA, short-acting.
|
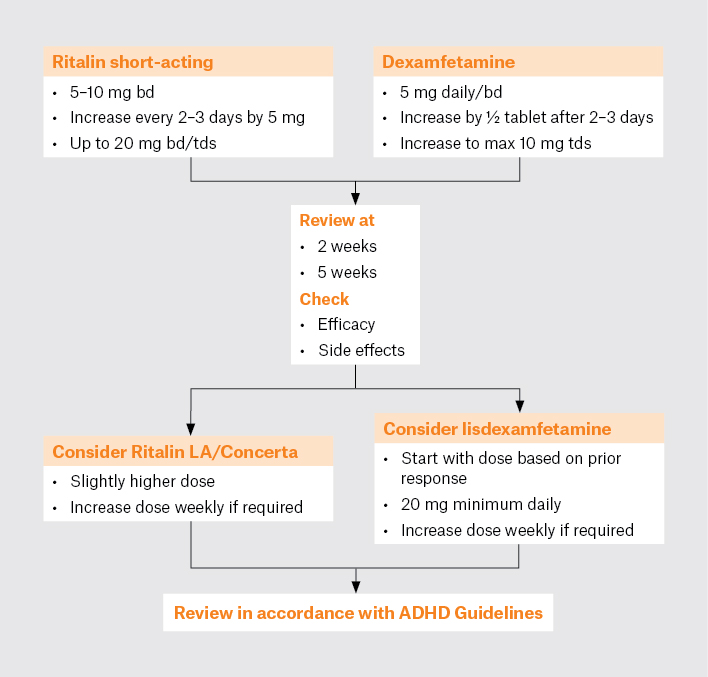
Figure 1. Example adult initiation protocols: Initiation with short-acting stimulant.
ADHD, attention deficit hyperactivity disorder; bd, twice per day; tds, three times a day.
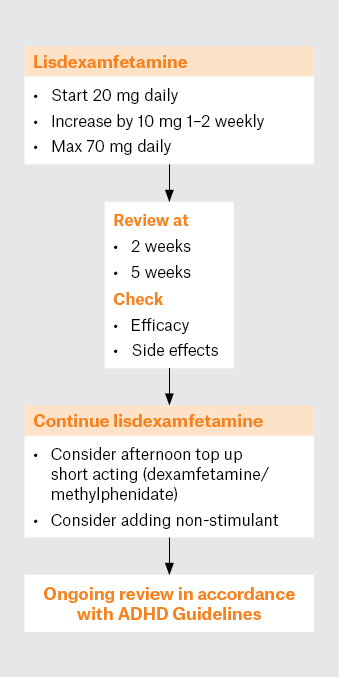
Figure 2. Example adult initiation protocols: Initiation with long-acting stimulant.
ADHD, attention deficit hyperactivity disorder.
|
Table 4. Example paediatric initiation protocols using 5 mg dexamfetamine or 10 mg methylphenidate immediate release tablets taken twice a day at breakfast and lunch2
|
|
Patient weight
|
Week 1
|
Week 2
|
Week 3
|
Week 4
|
|
20 kg
|
¼ + ¼
|
½ + ½
|
¾ + ¾
|
1 + 1
|
|
30 kg
|
½ + ½
|
1 + 1
|
1½ + 1
|
1½ + 1½
|
|
40+ kg
|
½ + ½
|
1 + 1
|
1½ + 1½
|
2 + 2
|
Patients, teachers or caregivers do not always report a clear subjective change, and improvements might instead be observed in daily functioning. This can make structured follow-up and collateral history particularly important. Instead, changes are often reflected in improved task completion, reduced overwhelm, or better emotional regulation. Often changes might be first noticed by family or friends rather than the person themselves. If the treatment has not improved functional outcome, then a switch in medication needs to be considered and a review assessment undertaken to exclude other comorbidities such as mood disorder, menopause/perimenopause, drug and alcohol use, or, if simple behavioural factors are affecting function (ie lack of sleep or regular food intake).
Practice point: Dose optimisation
Often when a dose increase does not improve functional outcomes, at this point some practitioners will reduce to the lower dose which might then be used for continuing treatment. Further, if increasing the dose does not result in efficacy lasting the entire day, patients might benefit from the use of an afternoon short-acting psychostimulant dose. In this case, a single dose might suffice. For patients with poor sleep, low dose clonidine in the evening might assist.
An adequate trial requires both sufficient dose optimisation and enough time to assess response. For stimulants, this might occur relatively quickly, whereas non-stimulants typically require a longer period (4–12 weeks) before full benefit can be assessed.2 Setting expectations early that dose adjustment is routine, rather than a sign of treatment failure, can improve engagement and reduce premature discontinuation.9
Practice point: Assessing for efficacy
In addition to asking a patient subjective questions regarding medication effect, rating scales, such as the Adult ADHD Self-Report Scale, or SNAP-IV for children, might be used to assess for efficacy.2
Across Australia, ADHD prescribing in general practice occurs within differing regulatory frameworks. Given the current changing regulatory environment, GPs are encouraged to check their local state or territory requirements prior to initiating Schedule 8 (S8) psychostimulants or other similarly controlled medication.
Practice point: Real time prescription monitoring
Please also refer to your state or territory’s requirement to check a patient’s prescription history on the appropriate real time prescription monitoring site. At the time of writing, each state has a different website that requires a GP to register patient prescriptions and the sharing of data between states is not guaranteed.
Monitoring and safety
Ongoing monitoring of ADHD symptoms is essential, particularly during initiation and dose adjustments.1,2 In general practice, this is typically pragmatic, with a focus on functional outcomes rather than symptom scores alone, recognising that medication effects extend beyond symptom reduction to broader functioning.10,11 Monitoring responsibilities should also be understood within local prescribing frameworks, including co-prescribing and shared-care arrangements where these apply. The ADHD Guidelines provide useful checklists to monitor for adverse events.2
Key areas to review include:
- Appetite, weight, exercise and sleep
- Mood and anxiety symptoms
- Weight
- Height (for paediatric patients)
- Cardiovascular parameters (blood pressure and heart rate).1,2
Most adverse effects are mild and occur early in treatment, but persistence or emergence at higher doses might signal the need for dose adjustment, formulation change or reconsideration of the treatment approach. Appetite suppression and insomnia are among the most common and can often be managed with practical strategies such as earlier dosing or structured meal planning.2
Practice point: Observations to check at each medication review
Blood pressure and heart rate should be checked each time and at least 6-monthly. For children, height and weight should also be regularly checked (6-monthly); for adults, weight should be checked in the same timeframe at a minimum. Full details can be found in the ADHD Guidelines.2
Current evidence from large population studies does not indicate an increased risk of serious cardiovascular events in individuals without known cardiac disease.12 Psychiatric adverse effects such as psychotic symptoms are uncommon, and misuse or diversion is reported in a minority of patients.9,13 Observational data suggest that initiation of ADHD medication is associated with lower all-cause mortality, particularly deaths from unnatural causes.14
When treatment is not working
Real-world data suggest that persistence with ADHD medication is variable, highlighting the importance of ongoing review and optimisation.9 A common challenge in practice is determining what to do when a patient reports limited benefit.
Before changing medication, it is important to consider whether:
- Dose has been adequately optimised
- Duration of action is appropriate
- Adherence has been consistent
- Expectations of treatment are realistic.
Optimisation of lifestyle factors, including sleep, nutrition, exercise and avoidance of substance use, is essential. In practice, more than one of these factors often contributes to symptoms and distinguishing between suboptimal dosing, poor fit of medication and unmet psychosocial needs can be challenging.
If response remains suboptimal to an initial stimulant, it is generally appropriate to trial the alternative stimulant class before moving to non-stimulant options; patients not responding to one class will often respond to another.2
Switching between stimulant classes typically involves ceasing one medication and initiating the alternative at a low dose, followed by re-titration based on clinical response and tolerability. The decision to switch should be guided by both symptom response and the pattern of effect across the day, including pharmacokinetic and pharmacodynamic factors such as onset, duration and offset, and the nature of adverse effects.2
Within stimulant classes, once an effective immediate-release methylphenidate dose over the first 4 hours has been established, intermediate-acting formulation (Ritalin LA) can usually be selected and dose-matched to provide more consistent symptom coverage across the day. Care should be taken when converting from short-acting to long-acting methylphenidate (Concerta; see ADHD Guidelines for details).2
In contrast, there is no universally accepted dose equivalence between dexamfetamine and lisdexamfetamine. While conversion guides exist, they should be approached with caution: clinical response varies considerably between individuals and switching should generally be approached as a new titration rather than a simple dose conversion.2
If stimulants are ineffective, poorly tolerated or not suitable, non-stimulant options such as atomoxetine, clonidine or guanfacine should be considered depending on the predominant symptom that the patient identifies, recognising their slower onset of action and different adverse effect profiles. Clonidine and guanfacine are commonly co-prescribed with stimulant medications when clinically indicated.1,2,7
Observational studies also suggest that ADHD medications are associated with both benefits and risks across behavioural and psychiatric outcomes, reinforcing the need for individualised treatment.9 Where there is ongoing uncertainty about diagnosis, significant comorbidity, or difficulty achieving a therapeutic response, escalation to non-GP specialist care is appropriate.
Practice point: Breaks from medication
Medication ‘holidays’ can be used, although evidence whether this benefits the patient is unclear.2 The main proposed benefit is to mitigate against effect on appetite, which is a potential side effect of the stimulant medications. Patients might also wish to reduce medication burden, so after stable dosing has been established, stimulant medication can be skipped on days when it is not needed. Medication holidays are not recommended for the non-stimulants which require continuous administration to maintain therapeutic benefit.
Balancing guideline recommendations with individual factors
The ADHD Guidelines recommend stimulant medications as first-line pharmacological treatment for most children, adolescents and adults with ADHD, reflecting their strong and consistent efficacy.1,2
In practice, however, medication decisions are influenced by a range of factors beyond efficacy alone. These factors include patient preference, comorbidities, tolerability, functional goals, and the regulatory and prescribing context within each jurisdiction.
Conclusion
Optimising ADHD medication initiation and management in general practice necessitates rigorous and consistent adherence to established clinical guidelines. These guidelines provide a critical foundation for care, ensuring evidence-based practice and patient safety. Within this structured framework, real-world care is further refined by individual patient response, tolerability and preference. GPs play a pivotal part in diligently monitoring treatment, supporting adherence and adjusting therapy over time, always within the parameters set by clinical recommendations. This approach requires a willingness to refine treatment iteratively, focusing on functional outcomes and collaborative care, rather than expecting an immediate or complete response. By integrating medication effectively within broader ADHD management across the lifespan, and upholding rigorous and consistent guideline adherence, positive outcomes can be achieved, particularly as access pathways and prescribing responsibilities continue to evolve.