Attention deficit hyperactivity disorder (ADHD) is estimated to affect approximately 6–7% of Australian children based on structured diagnostic interviews, although higher proportions screen positive on rating scales.1–3 ADHD can lead to academic difficulties, behavioural problems, strained relationships, financial stress and increased risk of mental health disorders.4,5 Despite this significant burden, access to timely ADHD assessment and treatment in Australia is limited.6 Public paediatric clinics and public mental health services in Australia might not accept ADHD as a primary referral, leaving families dependent on private specialists, many of whom have long waiting lists.6
A recent survey of Australian stimulant prescribers showed that 91% were paediatricians or psychiatrists, with very few child psychiatrists available.7 This creates a major bottleneck in specialist‑led care.8 ADHD might account for up to 50% of the paediatric outpatient workload, although this estimate is based on 2008 data.9 The Henry Review of health services for children, young people and families’ highlighted these pressures and recommended piloting new models of integrated care that allow general practitioners (GPs) to prescribe stimulant medication.10 This was with the aim of improving access and reducing demand on specialist services.
Primary‑care‑led ADHD management is common in Canada and the US, supported by structured training and clinical guidelines.11,12 In Australia, general practice training pathways have only recently emerged, with programs now being implemented in several states. These programs require timely evaluation to understand whether trained GPs can provide effective ADHD care and how such models might integrate with existing services. In 2023 we developed and piloted a model in the Nepean Blue Mountains Local Health District, New South Wales (NSW) in which GPs are trained to diagnose, initiate treatment and provide ongoing management for children and adolescents with uncomplicated ADHD.13 For this study, ‘uncomplicated ADHD’ refers to ADHD without severe psychiatric comorbidity, severe tic disorders or medical contraindications to stimulant prescribing. ADHD with oppositional defiant disorder (ODD) was not considered ‘complicated’.
General practitioner training
From February 2023 to May 2025, six GPs received 12 days of training (clinics) and four of these GPs started recruiting children to this study (Box 1). During their training, these four GPs saw and assessed 5–8 new patients (mean 6.5) and conducted 24–44 follow-up reviews (mean 36.7) over the 12 clinics.
The aim of this study was to describe diagnostic pathways, treatment patterns, medication response, wait times and referral outcomes among the first 207 children diagnosed with ADHD by these GPs.
|
Box 1. Study procedures
|
|
General practice training and competency assessment
|
- 12 days of clinical training at the ADHD clinic, involving supervised assessment, formulation of management plans and follow-up.
- Four-module ADHD course delivered by the lead investigator.
- Competency assessment: two case-based discussions evaluating diagnostic accuracy, understanding of prescribing criteria, monitoring of treatment effects and management of comorbidities.
- Ongoing education: community of practice with case discussions.
|
|
Stage 1: Diagnostic assessment of children with suspected ADHD
|
- Developmental, medical, family and educational history.
- Evaluation of impairment across settings.
- Physical examination including height, weight, blood pressure.
- ADHD rating scales from at least two informants (Appendix 1; available online only).
- Information requested from teacher (Appendix 4; available online only).
- Assessment against inclusion/exclusion criteria.
- Clinical evaluation of contraindications to a stimulant (psychiatric or medical).
|
|
Stage 2: Initial management and titration for newly diagnosed participants
|
- Appropriate non-pharmacological intervention focused on impairment.
- Review effects of non-pharmacological intervention.
- If significant impairment persists and family agree, trial of stimulant medication.
- Therapeutic response monitored from history (parent and child report).
- Therapeutic response monitored in external setting (usually school) using IOWA Conners ratings (Appendix 3; available online only) and/or written or verbal reports.
- Assessment of side effects including weight and blood pressure.
- Assessment/discussion of clinical response and decision regarding ongoing management.
|
|
Stage 3: Ongoing review (minimum 6-monthly)
|
- Evaluation of therapeutic effects as reported by parent and child.
- Evaluation of functioning at school based on verbal reports, written descriptions, ratings and/or school reports.
- Measurement of height, weight and blood pressure.
- Review of non-pharmacological interventions.
- Review and adjustment of dose or drug to optimise clinical benefit.
|
|
ADHD, attention deficit hyperactivity disorder.
|
Methods
Study design
This prospective cohort study evaluated an integrated model of ADHD care delivered in two general practices.
Ethical approval
The study was approved by Nepean Blue Mountains Human Research Ethics Committee (Ref 2020/ETH02503).
Participants
Participants were children aged 4–17 years who met the criteria for ADHD based on the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5)14 and NSW Ministry of Health prescribing criteria.15 All children who met diagnostic criteria at assessment by participating GPs and who had a clinical indication for a trial of medication were enrolled.
Consent
Written informed consent was obtained from parents for children, and from adolescents where appropriate.
Procedures: Diagnosis, management and follow-up
Stage 1: Diagnostic assessment of children with suspected ADHD
Assessment included detailed developmental history, functional history across settings, medical history and physical examination. The history obtained from the parent and child was supplemented with a questionnaire from the child’s teacher, rating the child’s functioning and performance in class compared to their peers, together with a space for recording any specific concerns. The clinical diagnosis of ADHD based on the history was confirmed with DSM-5 based ADHD rating scales from at least two informants – usually a parent and a teacher. The rating used was the Nepean ADHD Project Symptom Scale (NAPSS) (Appendix 1; available online only).16 This allows ADHD to be scored either as a categorical diagnosis (6/9 of the questions for inattention and/or 6/9 of the questions for hyperactivity-impulsivity scored as ‘pretty much’ or ‘very much’) or as a continuous variable (with a summed score from each question rated on a scale of zero to three). The NAPSS also has five unique questions relating to five modalities of functional impairment. Although subjective, these questions are considered the most clinically relevant.
Stage 2: Initial management and titration for newly diagnosed participants
Children with persistent impairment despite appropriate non‑pharmacological interventions were offered a trial of a stimulant medication using either dexamfetamine 5 mg or methylphenidate 10 mg tablets. Doses were increased weekly as tolerated to identify the optimal individualised therapeutic dose. The titration schedule took place over 4 weeks Appendix 2; available online only).17 All subsequent dose adjustments were based on clinical effects, not calculated based on weight.
Medication efficacy at school was monitored using the inattention hyperactivity with aggression (IOWA) Conners rating scale18 at baseline and after each dose change, using the form shown in Appendix 3 (available online only), which also invites free comments from the teacher. The IOWA Conners scale has five items relating to inattention/overactivity and five for oppositional/defiant behaviour. Each question is scored on a 4-point scale: 0 = not at all; 1 = just a little; 2 = pretty much; 3 = very much. The goal for effective treatment of ADHD is to achieve ratings within the ‘neurotypical’ range (mean score per item of <1.5).19 In cases where IOWA Conners scale ratings were not returned, descriptive confirmation of efficacy was sought from a teacher, therapist or coach, preferably in written form.
At review following dose titration, the initial medication could be continued at the dose considered optimal based on discussion with the parent and patient, the feedback from the teacher, and experience of side effects. Participants titrated successfully onto methylphenidate tablets might be offered a modified release formulation.
If a satisfactory response was not achieved with the first stimulant, titration might be repeated with the alternative stimulant.20 Participants aged over 6 years and more suitably treated with a once-daily formulation were prescribed lisdexamfetamine (prodrug of dexamfetamine) at 20 or 30 mg/day with dose increases at 2–4 weeks as required and tolerated to a maximum of 70 mg/day. This was also monitored with IOWA Conners scale ratings from the child’s teacher.
Non-stimulant medications such as guanfacine were prescribed as necessary.
Stage 3: Ongoing review
Stable participants were reviewed at least every 6 months. Reviews included physical measurements, assessment of functioning, review of non-pharmacological interventions and teacher feedback. Medication adjustments were made as necessary to maintain a favourable balance of therapeutic versus adverse effects.
Outcomes
- Primary outcomes: number of participants diagnosed and treated in primary care; treatment effectiveness.
- Secondary outcomes: referrals to non-GP specialists; patient/parent satisfaction (reported separately).
- Additional outcomes: recruitment sources, wait time, number of appointments and prescriptions in first 6 months.
Data collection and management
Data were entered into a study database in re-identifiable coded form. Identifying information was stored separately.
Statistical analysis
Data were analysed using the statistical program Statistical Package for the Social Sciences (SPSS) – IBM SPSS Statistics 26 (IBM Corporation). Descriptive statistics summarised participant characteristics. Continuous variables with skewed distributions are presented as medians and interquartile ranges. Paired t-tests were used for IOWA Conners scale scores.
Results
Characteristics of children diagnosed with ADHD in general practice
During July 2023 to February 2026, 207 children were diagnosed with ADHD in the two general practices in this study: 112 boys (54%); 91 girls (44%) and 4 non-binary (2%). Their mean age at enrolment was 11.36 (SD 3.88) years; range 4.08–17.86 years.
The type of ADHD was combined in 83 (40%), inattentive in 110 (53%) and hyperactive/impulsive in 14 (7%), with diagnostic concordance between the parent and teacher ratings in 32%. The main discrepancies were for children with combined type on the teacher ratings and inattentive ADHD on the parent ratings (21, 10%) and vice versa (20, 10%). ODD was more prevalent from parent than teacher ratings (101 [49%] vs 29 [14%]), with 55% concordance.
As of February 2026, 143 (69%) of those diagnosed in the participating practices were being treated with medication, including 22 still undergoing dose titration. Of 121 stabilised on medication, 118 (97.5%) were taking a stimulant. Eleven had ceased medication and 16 were no longer attending (Figure 1).
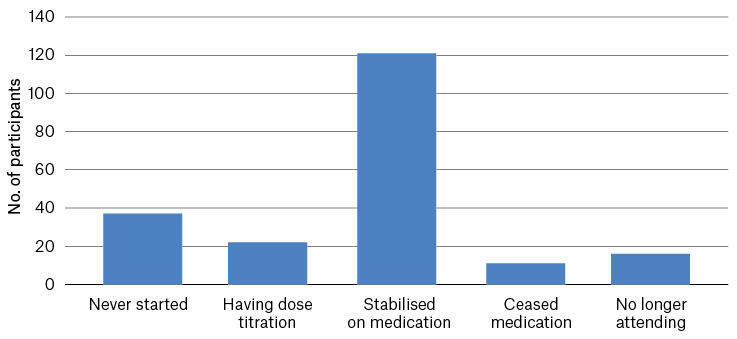
Figure 1. Current medication status of 207 participants diagnosed with attention deficit hyperactivity disorder in general practice in this study.
Medication efficacy
A total of 133 participants had one or more teacher IOWA Conners ratings (Table 1 and Appendix 3).18 Among the 85 with serial ratings there was a significant reduction in symptom scores after dose titration (−5.01 (SD 3.54), P<0.001 for inattention/overactivity; and −2.05 (SD 3.12), P<0.001 for oppositional/defiant). After dose titration the mean score inattention/overactivity was 2.32 (SD 2.38), which is 0.46 per item. At subsequent review, after a mean of 0.95 (SD 0.54) years, the mean score per item had risen slightly to 0.66 but remained <1.
|
Table 1. IOWA Conners teacher ratings in 133 children diagnosed and treated for attention deficit hyperactivity disorder in primary care who had at least one teacher rating
|
|
|
N
|
Score mean (SD)
|
Score per itemA
|
|
Inattention/overactivity at baseline
|
87
|
7.40 (3.82)
|
1.48
|
|
Inattention/overactivity after dose titration
|
103
|
2.32 (2.38)
|
0.46
|
|
Inattention/overactivity at follow-up
|
73
|
3.30 (3.34)
|
0.66
|
|
Oppositional/defiant at baseline
|
86
|
2.62 (3.59)
|
0.52
|
|
Oppositional/defiant after dose titration
|
103
|
0.71 (1.57)
|
0.14
|
|
Oppositional/defiant at follow-up
|
73
|
1.63 (3.07)
|
0.33
|
|
A The range of possible scores is 0–15 for inattention/overactivity and 0–15 for oppositional/defiant.
SD, standard deviation.
|
Five children (2.4%) were referred to non-GP specialists: two aged <10 years to paediatrics and three teenagers to psychiatry. One of these had not yet received medication for ADHD and three had their treatment ceased prior to referral. Reasons for referral included diagnostic uncertainty (n = 1), emerging mood/anxiety symptoms (n = 2), parental request for autism assessment (n = 1) and possible stimulant abuse (n = 1). No deaths or hospital admissions occurred.
Source of referrals and wait times
The principal referral source was from other general practices (118, 57%), but self-referral to a study GP was also common (49, 24%), as was referral from a GP colleague from the same practice (38, 18%); two (1%) were referred from nurse practitioners. The median wait time for a first appointment was 3 weeks.
GP management of ADHD in first 6 months of follow-up
Of the 207 children diagnosed in general practice in this study, 157 had been enrolled for more than 6 months by the end of 2025. Not all had returned for a follow-up appointment but of the 114 participants who had had a documented 6-month review, the median number of appointments during the first 6 months was 2 (interquartile range (IQR) 1–2) and median prescriptions 2 (IQR 1–2). Of the 105 receiving treatment at 6 months, 73 (70%) were on methylphenidate, 25 (24%) on lisdexamfetamine, 5 (5%) on dexamfetamine and 2 (2%) on guanfacine. Forty-five (43%) remained on their initial formulation, 44 (42%) had changed from an immediate release to a modified release formulation of methylphenidate, 13 (12%) had had one change and 3 (3%) had two changes of stimulant.
Discussion
This study provides preliminary Australian evidence that trained GPs may be able to diagnose and manage uncomplicated ADHD in children and adolescents.
Clinical effectiveness
Statistically significant improvements in teacher-rated symptoms were observed during titration, with sustained control at follow-up. These outcomes are consistent with improvements typically reported in structured ADHD titration pathways. For example, Coghill and Seth reported a mean item score for ADHD criteria after titration of 0.7 for the Dundee ADHD Clinical Care Pathway using a similar Likert scale.19 This compares well with our mean score of 0.66 per item for inattention/overactivity at follow-up.
Safety
No serious adverse events occurred, and stimulant prescribing was well tolerated. The low referral rate (2.4%) suggests that most children presenting with uncomplicated ADHD can be managed in primary care, reserving specialist services for complex cases.
Feasibility
The model substantially improved access, with a median wait time of only 3 weeks. In 2021 Mulraney et al investigated the wait times for private paediatricians and psychiatrists practising in Victoria or South Australia, for a hypothetical child presenting with either ADHD or anxiety. They found wait times were 44 and 41 days respectively; however, 34% of psychiatrists and 15% of paediatricians were unable to offer any appointment to such children. By contrast the appointment and prescribing patterns in our study appear to indicate that GP-led care is efficient and sustainable. High retention rates further support acceptability to families.
Implications for practice
This model offers a scalable solution to Australia’s ADHD treatment bottleneck.
With appropriate training and support, GPs can deliver high-quality ADHD care, reducing pressure on paediatric and psychiatric services and improving equity of access.
Strengths and limitations
Strengths include the prospective design, real-world general practice setting and use of validated outcome measures. The use of descriptive observational data to support medication decision making where ratings were not obtainable reflects pragmatic clinical practice. Limitations include incomplete teacher rating data, absence of a specialist comparison group and limited generalisability beyond one region. This study did not record the rate of diagnosis of those presenting with potential ADHD.
Further research
The high rate of recruitment from other general practices might, in the future, saturate the capacity of the GPs trained in ADHD management to continue to diagnose and treat new patients with ADHD. This should be evaluated over the longer term, together with pathways to facilitate transfer back to the referring GP for ongoing management. Future studies could look at the recruitment rate when compared to paediatric clinics.
Conclusion
These preliminary findings suggest that trained GPs may be able to provide safe, effective and accessible ADHD care for many children and adolescents. Larger studies with comparator groups are needed to confirm these findings and inform national ADHD service planning.