|
Table 1. Clinical features of the differential diagnoses of pityriasis versicolor1
|
|
Condition
|
Clinical features
|
|
Pityriasis versicolor
|
Hyperpigmented, hypopigmented or erythematous macules and patches with fine scale, typically distributed over the trunk and proximal limbs
|
|
Confluent and reticulated papillomatosis
|
Reticulated hyperpigmented scaly patches usually affecting the trunk and neck
|
|
Patch-stage mycosis fungoides
|
Erythematous patches with fine wrinkling, resembling ‘cigarette paper’, commonly involving the trunk in a bathing suit distribution
|
|
Seborrhoeic dermatitis
|
Erythematous plaques with greasy yellow scale; affects seborrhoeic areas such as the trunk, scalp, eyebrows and nasolabial folds
|
|
Pityriasis rosea
|
Erythematous macules and patches with a collarette of scale, in a ‘Christmas tree-like’ distribution, often preceded by a herald patch. Typically self-resolving
|
|
Erythrasma
|
Well-demarcated erythematous or hyperpigmented patches typically seen in the intertriginous areas, such as the axillae and groin, showing coral pink fluorescence under Wood’s lamp
|
|
Pityriasis alba
|
Hypopigmented macules and patches with fine scale, commonly seen on the face and upper limbs of children
|
|
Vitiligo
|
Well-demarcated depigmented macules and patches without scale
|
Answer 2
PV can usually be diagnosed clinically on the basis of the characteristic hypopigmented, hyperpigmented or erythematous macules and patches with fine scale, typically distributed over the trunk and proximal limbs.1 Gentle stretching of the affected skin might accentuate the fine scale, a finding known as the evoked scale sign.2 This sign is considered diagnostic for PV and helps distinguish it from other pigmentary disorders such as post-inflammatory hyperpigmentation, which typically lack scale. In addition, Wood’s lamp examination might demonstrate a characteristic yellow– orange fluorescence.3
Answer 3
Direct microscopy of skin scrapings with potassium hydroxide (KOH) preparation can confirm the diagnosis, demonstrating fungal hyphae and spores with the characteristic ‘spaghetti and meatballs’ appearance.2 This simple and minimally invasive test is preferable to a skin biopsy, which might leave scars, particularly in patients with skin of colour.
Case continued
Gentle stretching of the skin accentuated the fine scale, consistent with the evoked scale sign (Figure 2). Fluorescence staining of skin scrapings revealed fungal hyphae and spores with a characteristic ‘spaghetti and meatballs’ appearance (Figure 3), confirming a diagnosis of PV.
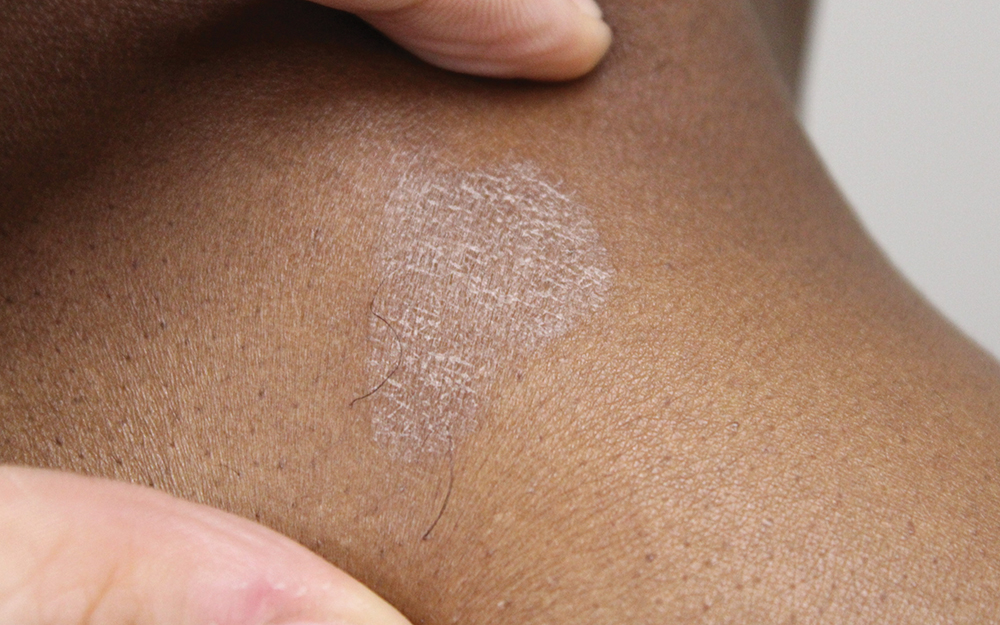
Figure 2. Gentle skin stretching accentuated the fine scale, consistent with the evoked scale sign.
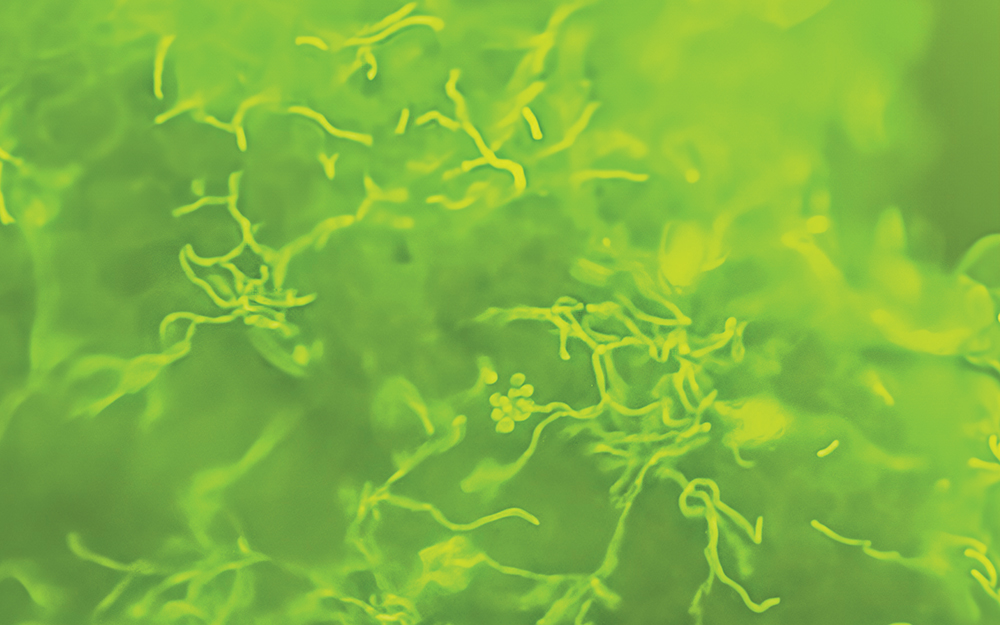
Figure 3. Fluorescence staining of skin scrapings revealed a ‘spaghetti and meatballs’ appearance, which is diagnostic of pityriasis versicolor.
Question 4
How does PV present differently in patients with skin of colour?
Question 5
What is the management of PV?
Answer 4
Although some studies have shown that hypopigmented PV is more common in patients with skin of colour, both hypopigmented and hyperpigmented variants can occur.1,4 In patients with skin of colour, hyperpigmented lesions tend to appear dark brown to grey–black, whereas the lesions are more often light tan or salmon-coloured in patients with lighter skin colour.5 In addition, post-inflammatory pigmentary changes might persist after clearance of infection and can be a significant source of concern in patients with skin of colour.6
Answer 5
It is important to optimise risk factors for PV, including maintaining good hygiene practices such as showering after exercise and washing clothes regularly.6,7 Patients should be reassured that PV is not contagious. According to Therapeutic Guidelines, the first-line treatment for PV includes econazole 1% solution once daily at night for 3 nights, ketaconazole 2% shampoo daily for 5 days or selenium sulphide 2.5% shampoo daily for 7–10 days.7 Econazole 1% solution should be applied after showering to the affected area and left on overnight, then washed off the next morning. Medicated shampoos should be applied to damp skin and left on for 5–10 minutes before rinsing off.
A stat dose of 400 mg oral fluconazole might be considered in severe, treatment- resistant cases.7 Of note, treatment with griseofulvin and terbinafine is ineffective for PV.7 Patients should be counselled that the endpoint of treatment is resolution of scale rather than disappearance of pigmentary change, as pigmentary alteration might persist for many months after successful treatment, particularly in patients with skin of colour.6 Recurrence of PV is common, with relapse rates reported as high as 80%, highlighting the importance of maintenance treatment.6 Preventive regimens include the intermittent use of anti-fungal shampoos or soaps containing selenium sulphide, zinc pyrithione or ketoconazole.6
Case continued
The patient’s condition resolved with topical econazole nitrate 1% treatment, applied nightly for 3 days. Remission was maintained with ketoconazole 2% shampoo twice weekly as maintenance therapy.
Key points
- The evoked scale sign is a useful bedside finding that is diagnostic of PV.
- Patients should be counselled that the treatment endpoint is resolution of scale, whereas pigmentary changes might persist, particularly in patients with skin of colour.
- Maintenance therapy with anti-fungal shampoo is important to reduce relapses.